
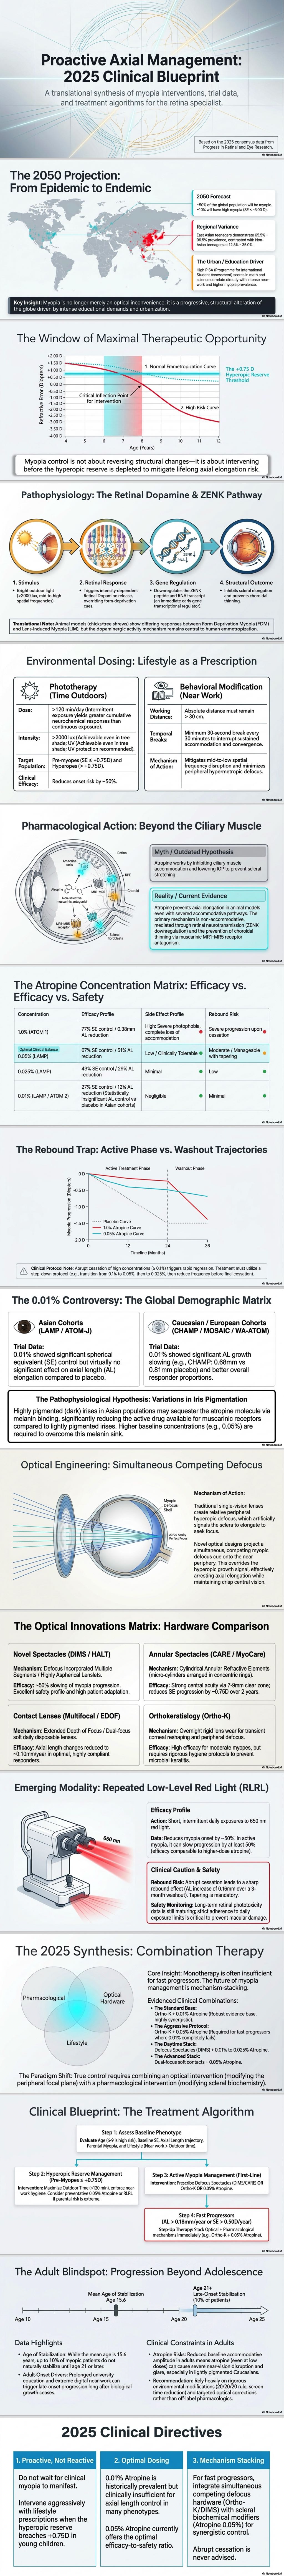
The world is currently facing a silent but rapid public health crisis: the alarming rise of childhood myopia. Current projections suggest that by the year 2050, nearly half of the global population will be myopic, with approximately one-tenth suffering from high myopia (SE ≤ -6.00 D). This is not merely a matter of needing stronger glasses; myopia is marked by increased axial elongation (the eye growing too long), which significantly raises the risk of sight-threatening complications such as myopic macular degeneration (MMD), glaucoma, and even blindness.
Fortunately, the latest research—culminating in major clinical insights for 2025—has provided a robust toolkit for clinicians and parents to slow down this progression. From simple lifestyle shifts to high-tech red-light therapy, here is a comprehensive breakdown of the current state of myopia management.
1. The Foundation: Lifestyle and Environmental Interventions
Before moving to medical treatments, the most critical (and cost-effective) interventions involve changing how we interact with our environment.
The Power of Outdoor Time
Spending time outdoors is the simplest and most effective lifestyle intervention for at-risk children.
- The Mechanism: Natural light exposure triggers the release of dopamine in the retina, a light-driven neurohormone that acts as a “stop” signal for axial eye growth.
- The Goal: Research indicates that at least 2 hours of outdoor time per day can eliminate the additional risk associated with myopic parents.
- The Lux Factor: While animal studies require massive light intensity, evidence suggests that 2,000 to 5,000 lux—achievable even in the shade of a tree—is effective for humans.
- Prevention vs. Progression: Increasing outdoor time can reduce the incidence of myopia by up to 50% in non-myopic children. However, its effectiveness in slowing progression once a child is already myopic is less pronounced, though still beneficial as a complementary habit.
Managing Near Work and Digital Devices
The “near work” hypothesis has been debated for 400 years, but 2025 data confirms that it’s not just how long you read, but how you read.
- Charateristics of Risk: Reading at a distance of less than 30 cm and reading continuously for more than 30 minutes independently raise myopia risk.
- The Digital Surge: Smartphones are particularly “myopiagenic” because they are held closer to the eyes and involve flickering, engaging content that creates a sustained stimulus for axial elongation.
- The Rule of Thumb: Clinicians now recommend keeping a viewing distance >30 cm and taking frequent breaks.
2. Pharmacological Interventions: The Atropine Revolution
Atropine eye drops have been the gold standard for myopia control for decades, but the focus has shifted from high-dose to low-concentration formulations to minimize side effects.
The “Sweet Spot” of Concentration
The LAMP (Low-concentration Atropine for Myopia Progression) Study was pivotal in identifying the optimal balance between safety and efficacy.
- 0.05% Atropine: This concentration has emerged as a high-performer, reducing myopia progression by 67% and axial elongation by 51% over one year.
- 0.01% Atropine: While common, this concentration has shown modest to no effect on axial eye growth in some studies, particularly in Asian populations.
- The Rebound Effect: High concentrations (0.5%–1.0%) are effective but cause significant rebound (rapid progression once drops are stopped) and side effects like glare and blurred near vision.
- Prevention: The LAMP-2 study showed that nightly use of 0.05% atropine in non-myopic children with a family history of myopia reduced the cumulative incidence of the condition by 46.4%.
Future Candidates
While atropine leads the way, other pharmacological agents are under investigation:
- 7-Methylxanthine (7-MX): A caffeine metabolite approved in Denmark that targets scleral collagen to strengthen the eye.
- Crocetin and Omega-3s: Dietary supplements that may offer safe, non-invasive ways to inhibit eye growth by improving choroidal blood flow.
3. Optical Interventions: Novel Lenses and Contacts
Modern optics use the “simultaneous competing defocus” theory. By providing clear central vision while creating myopic defocus in the periphery, these lenses signal the eye to stop growing.
Myopia Control Spectacle Lenses
New spectacle designs have replaced traditional bifocals with high-tech lenslet arrays:
- DIMS (Defocus Incorporated Multiple Segments): Marketed as MiYOSMART, these lenses feature a honeycomb-like pattern of lenslets. They can slow progression by 52% and axial growth by 62%.
- HALT (Highly Aspherical Lenslets Target): Marketed as Stellest, these use concentric rings of lenslets. Full-time wearers in a 2-year trial saw a 67% reduction in progression.
- DOT (Diffusion Optics Technology): These lenses scatter light to reduce peripheral contrast, based on the theory that high-contrast urban environments overstimulate eye growth.
Contact Lens Options
For active children, contact lenses provide constant treatment regardless of eye movement.
- Dual-Focus Lenses (MiSight): The first FDA-approved daily disposable for myopia control. A 6-year study showed sustained efficacy with no evidence of rebound after stopping.
- Orthokeratology (Ortho-K): These are overnight-wear rigid lenses that temporary reshape the cornea. They provide daytime visual freedom and slow axial elongation by 32%–59%. Efficacy is enhanced when the lens has a smaller treatment zone (BOZD).
4. The Cutting Edge: Repeated Low-Level Red Light (RLRL)
Perhaps the most exciting development in 2025 is RLRL therapy. This involves a child looking into a desktop device that emits a specific wavelength (650 nm) for 3 minutes, twice a day.
- Exceptional Efficacy: Large trials have found that RLRL can slow SE progression by 76.6% and axial elongation by 69.4%.
- Axial Shortening: Remarkably, up to 21.85% of children treated with RLRL experienced actual shortening of the eye, a phenomenon almost never seen with other treatments.
- Safety Monitoring: While generally safe and standardized as “no light hazard,” long-term data is still being collected. Clinicians must monitor for rare instances of retinal structure changes.
5. When Monotherapy Fails: Combination Treatments
For “fast progressors” or children with high-risk profiles, combining treatments can yield better results by targeting multiple biological pathways.
- Ortho-K + 0.01% Atropine: This is the most well-evidenced combination, showing superior slowing of axial elongation compared to Ortho-K alone.
- Lenses + Atropine: Combining DIMS or HALT lenses with low-concentration atropine (0.01%–0.05%) has shown an additive effect, significantly reducing progression in children who were not responding well to a single treatment.
- Red Light + Ortho-K: For children poorly responding to Ortho-K monotherapy, adding RLRL has been shown to induce axial shortening and improve control.
6. Myopia in Adults: A Growing Interest
While myopia usually stabilizes by age 16, adult-onset myopia is increasingly common, affecting 5%–14% of young adults annually.
- Risk Factors: Asian ethnicity, parental history, and intensive academic environments (e.g., law or medical school) are major drivers.
- Post-Surgical Progression: Adults who have had LASIK or PRK may still experience axial elongation, leading to a “re-emergence” of myopia years later.
- Treatment Gap: There is currently limited research on myopia control in adults, though lifestyle recommendations (more outdoor time, less near work) remain essential.
Conclusion: The Path Forward
The success of myopia management in 2025 hinges on personalization. A child’s age, baseline refraction, and family history must all be considered when choosing a treatment.
Key Takeaways for Parents and Clinicians:
- Start Early: Interventions are most effective when children still have their “hyperopic reserve” (mild far-sightedness).
- Outdoor Time is Essential: Aim for 2 hours daily as a non-negotiable health habit.
- Monitor Compliance: Whether it’s eye drops or glasses, the benefits are dose-dependent.
- Don’t Settle for Standard Glasses: If a child’s myopia is progressing, single-vision lenses are no longer the standard of care.
By embracing these evidence-based strategies, we can move from simply correcting vision to actively protecting the long-term ocular health of the next generation.
Reference
Yam, J. C., Zhang, X. J., Zaabaar, E., Wang, Y., Gao, Y., Zhang, Y., Li, X., Kam, K. W., Tang, F., Chu, W. K., Zhou, X., Zhang, W., He, X., Wu, P.-C., Rose, K. A., Morgan, I., He, M., Ohno-Matsui, K., Jonas, J. B., Zhang, M., Tham, C. C., Chen, L. J., & Pang, C. P. (2025). Interventions to reduce incidence and progression of myopia in children and adults. Progress in Retinal and Eye Research, 109, 101410.
Optimizing Myopia Management: The Nonlinear Efficacy and Threshold of Atropine Dosing
The global surge in myopia prevalence, particularly in East Asia, has transformed it from a simple refractive error into a significant public health threat. For retina specialists, the concern lies not in the diopters themselves, but in the excessive axial elongation associated with myopia, which drastically increases the lifetime risk of sight-threatening complications such as retinal detachment, myopic choroidal neovascularization, and macular staphyloma. While various interventions exist, atropine eye drops have emerged as a primary pharmacologic strategy to slow this progression. However, the clinical community has long struggled with a fundamental question: what is the optimal concentration?. A landmark systematic review and dose-response meta-analysis by Zhang et al., published in Survey of Ophthalmology, provides critical insights into the efficacy, tolerability, and threshold effect of various atropine doses, offering a data-driven roadmap for clinical practice.
The Study Framework: A Robust Meta-Analysis
This comprehensive study analyzed 33 randomized clinical trials (RCTs) involving 6,301 children aged 4–18 years. The analysis covered a wide spectrum of ten different atropine concentrations, ranging from as low as 0.0025% to as high as 1%. To move beyond simple pairwise comparisons, the researchers employed restricted cubic spline (RCS) models to evaluate the continuous dose-response relationship. This methodological choice allowed for the identification of nonlinear trends that traditional meta-analyses might overlook. The primary outcomes focused on the annual change in spherical equivalent refraction (SER) and axial length (AXL) elongation, while secondary outcomes assessed tolerability through pupil diameter, accommodation amplitude (AA), and adverse events like photophobia.
The Nonlinear Reality: Efficacy vs. Concentration
The core finding of the research is the existence of a statistically significant nonlinear relationship between atropine dosage and treatment efficacy (P < 0.001). Contrary to the assumption that “more is always better,” the efficacy curve demonstrates a sharp initial increase at low concentrations followed by a pronounced plateau.
For Spherical Equivalent Refraction (SER) progression, the mean differences compared to placebo were:
- 0.01% Atropine: 0.21 D reduction per year (95% CI, 0.13–0.28).
- 0.02% Atropine: 0.35 D reduction per year (95% CI, 0.23–0.46).
- 0.05% Atropine: 0.46 D reduction per year (95% CI, 0.31–0.61).
- 0.1% Atropine: 0.49 D reduction per year (95% CI, 0.34–0.63).
Crucially, increasing the concentration from 0.05% to 0.1%—a doubling of the dose—yielded a marginal gain of only 0.03 D per year. This indicates that the therapeutic benefit begins to plateau beyond the 0.05% threshold.
The data for Axial Length (AXL) elongation, which is of paramount importance to retina specialists, followed a similar nonlinear trajectory (P < 0.001). The reduction in annual AXL elongation was:
- 0.01% Atropine: -0.07 mm (95% CI, -0.11 to -0.04).
- 0.05% Atropine: -0.16 mm (95% CI, -0.24 to -0.09).
- 0.1% Atropine: -0.17 mm (95% CI, -0.24 to -0.11).
Again, the transition from 0.05% to 0.1% resulted in an almost negligible additional reduction in axial growth (-0.01 mm). While higher concentrations like 0.5% and 1% did show further reductions in AXL (-0.24 mm and -0.33 mm, respectively), these estimates were derived from fewer and smaller trials, requiring cautious interpretation.
Safety, Tolerability, and the Patient Experience
While efficacy plateaus, the side effect profile continues to follow a more linear and dose-dependent path. The study highlights that higher doses are significantly associated with:
- Decreased Accommodation Amplitude (AA): A linear decrease was observed as doses increased (P = 0.02). For example, 0.05% atropine resulted in a mean reduction in AA of -1.66 D to -2.34 D compared to placebo.
- Increased Pupil Diameter: Both photopic and mesopic pupil diameters increased with higher concentrations. A nonlinear relationship was specifically noted for photopic pupil diameter (P = 0.03), where the impact on light sensitivity is most acutely felt by the patient.
- Frequency of Photophobia: There was a clear linear increase in reported photophobia as the dose rose (P = 0.02). The pooled frequency of photophobia was 8.2% for 0.01% atropine, rising to 15.4% at 0.05%, and jumping to 22.0% at 0.5%.
Interestingly, the meta-analysis found no significant differences in distance or near best-corrected visual acuity (BCVA) or the frequency of allergic conjunctivitis across the low-concentration spectrum (up to 0.05%), suggesting that these specific parameters are relatively stable at these doses.
Clinical Implications: Moving Beyond “Step-Up” Dosing
The identification of a threshold effect has profound implications for clinical practice. Currently, many clinicians utilize a stepwise dosing strategy, increasing the concentration of atropine for children who show an “inadequate response” to lower doses like 0.01%. The findings of this meta-analysis challenge this approach.
Because efficacy significantly slows beyond 0.05%, doubling the dose to 0.1% or higher in a “poor responder” may increase the risk of side effects—such as blurred near vision and glare—without providing a meaningful increase in myopia control. Instead of monotherapy dose escalation beyond this range, the authors suggest that clinicians should prioritize optimizing treatment strategies within the 0.01% to 0.05% range or exploring combination therapies (e.g., atropine plus defocus spectacles or orthokeratology).
Special Considerations: Ethnicity and COVID-19
The study also shed light on how external factors and demographics influence treatment outcomes:
- Ethnicity: Most robust data currently exists for East Asian populations. Subgroup analysis showed that 0.01% atropine was more effective in Asian children (0.22 D reduction) compared to Caucasian children (0.12 D reduction) (P < 0.001). This highlights the need for further research in diverse ethnic groups to determine if the 0.05% threshold applies universally.
- The COVID-19 Pandemic: Myopia progression accelerated during the pandemic due to lockdowns and increased near-work. The meta-analysis confirmed that 0.01% atropine was less effective during pandemic periods compared to non-pandemic periods, likely due to these overwhelming environmental stressors.
Conclusion for the Retina Specialist
For those of us managing the long-term retinal consequences of high myopia, these data provide a vital piece of the preventative puzzle. We now know that atropine efficacy is nonlinear and that the current clinical “sweet spot” for maximizing efficacy while maintaining tolerability appears to reside at or near the 0.05% concentration.
Increasing doses beyond 0.05% for children who continue to progress should be approached with extreme caution, as the therapeutic gain is minimal compared to the increased burden of side effects. By understanding these dosing thresholds, we can better guide our pediatric colleagues and patients toward more effective, personalized, and tolerable myopia management, ultimately reducing the future burden of myopic retinal degeneration.

Reference: Xiu Juan Zhang, Mingming Liu, Marco Yu, et al. Efficacy, tolerability, and threshold effect of atropine eye drops for myopia control: A systematic review and dose-response meta-analysis. Survey of Ophthalmology. 2026..


