
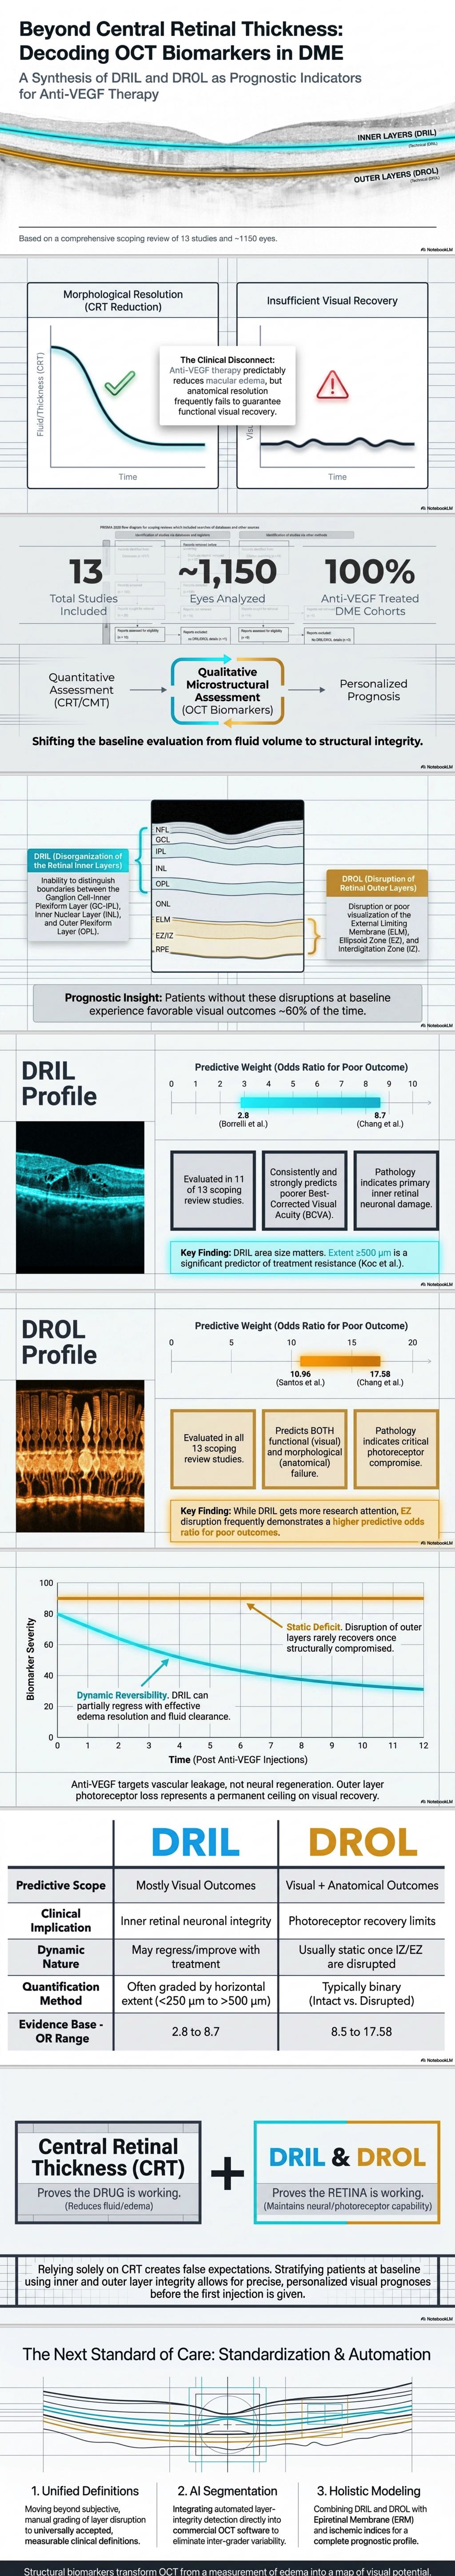
For the modern retina specialist, the management of Diabetic Macular Edema (DME) has been revolutionized by intravitreal anti-vascular endothelial growth factor (anti-VEGF) therapy. While these agents are the undisputed gold standard, every clinician has encountered the “anatomical-functional paradox”: a patient whose central macular thickness (CMT) returns to near-normal levels, yet their visual acuity remains stubbornly poor. This disconnect underscores the limitations of using CRT or CST as the sole metric for success.
To bridge this clinical gap, recent research has pivoted toward qualitative structural biomarkers on Optical Coherence Tomography (OCT). A recent scoping review has synthesized the evidence on two pivotal indicators: Disorganization of the Retinal Inner Layers (DRIL) and Disruption of the Retinal Outer Layers (DROL). These biomarkers offer more than just a snapshot of current edema; they provide a window into the underlying neural and photoreceptor integrity of the retina.
Defining the Neural Landscape: DRIL and DROL
Disorganization of the Retinal Inner Layers (DRIL) DRIL is technically defined as the inability to identify the boundaries between the ganglion cell-inner plexiform layer (GCL-IPL) complex, the inner nuclear layer (INL), and the outer plexiform layer (OPL). This loss of stratified architecture is proposed as a direct indicator of neural tissue damage. In a clinical setting, DRIL is typically assessed within the central 1 mm foveal zone. It has emerged as a robust predictor of visual outcomes, reflecting the disruption of horizontal, bipolar, and amacrine cells that facilitate signal transmission.
Disruption of the Retinal Outer Layers (DROL) While DRIL focuses on the inner circuitry, DROL (and its components) addresses the “engine” of vision: the photoreceptors. DROL encompasses the disruption or poor visualization of the External Limiting Membrane (ELM), the Ellipsoid Zone (EZ), and the Interdigitation Zone (IZ). These layers are essential for photoreceptor survival and function; thus, their integrity is a prerequisite for high-quality visual recovery. Notably, while many studies evaluate EZ and ELM integrity separately, the term “DROL” is increasingly used to describe the collective disruption of these vital outer structures.
The Predictive Power: Functional Outcomes and Non-Response
The scoping review included 13 studies covering approximately 1,150 eyes, providing a comprehensive look at how these markers dictate the anti-VEGF response.
1. DRIL as a Sentinel for Functional Failure DRIL was evaluated in 11 out of the 13 included studies and was consistently associated with poorer visual outcomes. Studies reported that the presence of DRIL at baseline significantly increases the odds of a poor functional response:
- The CHARTRES Study identified an odds ratio (OR) of 7.05 for DRIL in predicting poor best-corrected visual acuity (BCVA) gain.
- Other cohorts reported even higher probabilities, with an OR of 8.69 for functional non-response when DRIL is present.
- Interestingly, the persistence of DRIL after treatment is as significant as its baseline presence. In eyes where DRIL remained after 20+ injections, VA gains were minimal despite significant edema reduction.
2. DROL: The “Hard Ceiling” of Visual Recovery While DRIL is a powerful predictor, DROL components (specifically the EZ and ELM) often show an even stronger correlation with visual potential.
- In a multivariate model, the CHARTRES Study found that EZ disruption had a higher OR (10.96) than DRIL (7.05) for predicting poor visual outcomes.
- Evidence suggests that while the inner layers might show some “plasticity” or partial recovery, outer retinal disruption—particularly involving the IZ—is often static. Once these layers are compromised, the biological capacity for visual improvement reaches a functional ceiling.
The Paradox of Anatomical Success
One of the most critical takeaways for retina specialists is the weak correlation between CRT reduction and visual improvement in the presence of these biomarkers.
- Wirth et al. demonstrated that while CRT improved significantly (from 451.5 µm to 288.7 µm) after long-term therapy, microstructural damage (DRIL/EZ) remained largely unchanged, resulting in disappointing visual gains.
- Eraslan et al. further confirmed that DRIL and EZ irregularities are independent predictors of poor vision even after the successful resolution of macular edema.
This suggests that our clinical definition of a “responder” needs to evolve. A patient may be an anatomical responder (fluid resolution) but a functional non-responder (poor VA) due to underlying structural biomarkers.
Dynamic vs. Static Markers: Timing Matters
Understanding the temporal behavior of these biomarkers is essential for long-term prognosis:
- DRIL is a dynamic biomarker. Studies have shown that DRIL can regress or improve in patients who respond well to treatment. A reduction in the horizontal extent of DRIL (e.g., from >500 µm to a smaller area) is often associated with better VA gains.
- DROL is often a static biomarker. While some studies show EZ restoration (35.4% of patients in one study), DROL is generally less likely to recover post-treatment compared to DRIL.
Integrating Biomarkers into Clinical Practice
How should these findings change our daily practice? The review supports a more personalized approach to DME management:
- Patient Counseling: Identifying baseline DRIL or DROL allows for more realistic expectations. Patients with extensive EZ disruption or >500 µm of DRIL should be counseled that while injections will reduce fluid, their “vision potential” may be limited by existing neural damage.
- Evaluating Treatment Resistance: If a patient shows an asymmetric response to anti-VEGF, look for ELM disruption. It has been identified as the strongest predictor of resistance to therapy, even more so than the presence of epiretinal membranes (ERM).
- Beyond the CMT Number: Shift the focus from quantitative (thickness) to qualitative (integrity). An intact ELM and EZ, combined with the absence of DRIL, are the triad for a “good responder”.
Future Frontiers: AI and Standardization
The scoping review highlights several gaps that must be addressed to bring these biomarkers into the clinical mainstream. Currently, the definitions of DRIL and DROL can vary across studies, and most assessments remain manual and subjective.
The path forward involves standardized definitions and the integration of Artificial Intelligence (AI)-based segmentation tools into OCT software. Automated quantification of DRIL extent and EZ integrity would allow for more precise longitudinal monitoring and could eventually be used to trigger switches in therapy (e.g., from anti-VEGF to steroids) earlier in the disease course.
Conclusion
For retina specialists, DRIL and DROL are no longer just academic concepts; they are essential tools for predicting the functional lifespan of the diabetic retina. While anti-VEGF agents effectively target the vascular “leak,” they are limited in their ability to reverse established neuronal or photoreceptor damage. By incorporating these structural biomarkers into our routine OCT interpretation, we can provide more accurate prognoses, manage patient expectations, and move toward a truly personalized model of DME care.
Reference
Nadimpalli S, Vijendran S, Bhandary SV. Disorganization of inner retinal layers and disruption of outer retinal layers as predictors of anti-vascular endothelial growth factor treatment outcomes in diabetic macular edema: A scoping review. Survey of Ophthalmology. 2026. doi: 10.1016/j.survophthal.2026.05.005.


