
For decades, retina specialists have relied on a fundamental, visually intuitive axiom when grading diabetic retinopathy (DR): the more lesions you see, the more severe the disease. The foundation of the Early Treatment Diabetic Retinopathy Study (ETDRS) severity scale is built upon the meticulous counting and grading of microaneurysms, intraretinal hemorrhages, venous beading, and intraretinal microvascular abnormalities (IRMAs). We are trained to view a retina heavily dotted with these red lesions as a retina at high risk for progression to proliferative diabetic retinopathy (PDR).
However, what happens when the ischemic process becomes so profound that the capillary beds themselves completely close off? The hallmark lesions that we rely upon for staging—which reside within these capillary networks—are obliterated, resulting in an unremarkably quiet or “featureless” appearance on color fundus photography (CFP). This phenomenon, briefly referenced in Ryan’s Retina but historically underexplored in peer-reviewed literature, creates a dangerous clinical trap.
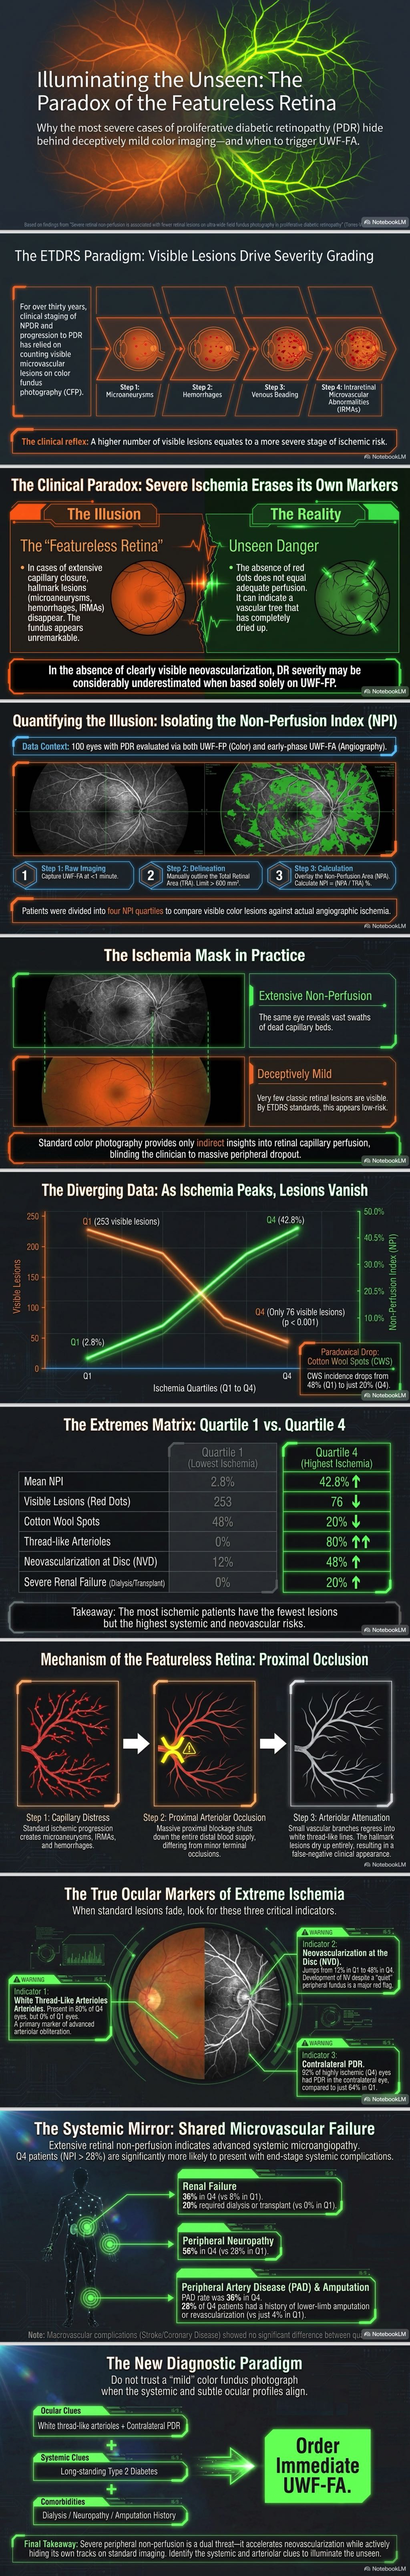
A compelling new retrospective study by Torres-Villaros et al. meticulously unravels this paradox, offering critical insights that should prompt retina specialists to rethink how they evaluate high-risk diabetic patients. By correlating the non-perfusion index (NPI) on ultra-wide field fluorescein angiography (UWF-FA) with lesion counts on ultra-wide field fundus photography (UWF-FP), the researchers have provided quantitative proof that the most ischemic retinas often exhibit the fewest visible lesions.
Here is a comprehensive deep dive into the study’s findings, the proposed pathophysiological mechanisms, and the crucial systemic red flags that can help you identify the featureless retina before vision-threatening complications occur.
Unpacking the Data: High Ischemia, Low Lesion Burden
To understand this paradox, the researchers at Avicenne Hospital evaluated 100 treatment-naïve eyes from 100 patients diagnosed with PDR via UWF-FA. Two blinded retina specialists calculated the NPI by dividing the manually delineated non-perfusion area (NPA) by the total analyzable retinal area (TRA) on early-phase UWF-FA. They also counted red dots (microaneurysms, hemorrhages, IRMAs), cotton-wool spots (CWS), venous beading, and white thread-like arterioles on corresponding UWF-FP images.
The eyes were divided into quartiles based on their NPI. The mean NPI values across the quartiles demonstrated a massive spectrum of ischemic burden:
- Quartile 1 (Mildest Ischemia): 2.8 ± 1.1%
- Quartile 2: 8.5 ± 2.1%
- Quartile 3: 17.3 ± 4.5%
- Quartile 4 (Severe Ischemia): 42.8 ± 12.2%
The Core Finding: The researchers discovered a stark inverse relationship between the extent of capillary non-perfusion and the number of visible microvascular lesions on color imaging. Eyes in Quartile 4—which had an astonishing average of nearly 43% of their analyzable retina devoid of perfusion—exhibited significantly fewer red dots (average of 76.1) compared to Quartile 1 (average of 253.0).
This 70% reduction in visible red dots in the most ischemic eyes occurred relatively uniformly across both the central ETDRS fields and the periphery.
Despite having far fewer visible markers of NPDR, the Quartile 4 eyes harbored significantly more aggressive neovascularization, displaying an average of 5.5 neovascular lesions compared to 2.1 in Quartile 1.
Furthermore, neovascularization at the disc (NVD)—a classic sign of widespread, severe ischemia—was present in 48.0% of Quartile 4 eyes versus only 12.0% in Quartile 1.
These findings confirm that in the late stages of diabetic microangiopathy, extensive capillary closure essentially “wipes the retina clean” of microaneurysms and hemorrhages, masking a highly advanced, proliferative state.
Pathophysiological Clues: Missing Cotton-Wool Spots and Thread-Like Arterioles
The featureless retina is not entirely without visual clues, provided the clinician knows exactly what to look for. The study highlighted two major morphological deviations in highly ischemic eyes that diverge from traditional ETDRS risk paradigms.
1. The Disappearance of Cotton-Wool Spots (CWS) Interestingly, patients in the highest NPI quartile exhibited significantly fewer CWS than those in the lowest quartile (20.0% vs. 48.0%).
This is a highly novel finding, as the sudden appearance of multiple CWS is typically viewed as a harbinger of rapid progression to PDR.
CWS are generally understood to represent focal ischemia in the superficial capillary plexus resulting from precapillary or terminal arteriolar occlusions, leading to ganglion cell axon stasis. The authors hypothesize that in cases of extreme, widespread retinal non-perfusion, the occlusive process may move more proximally.
Instead of terminal arteriolar occlusions, these eyes may suffer from major proximal arteriolar occlusions, fundamentally altering the ischemic presentation and preventing the classic formation of CWS.
2. The Rise of White Thread-Like Arterioles If red dots and CWS disappear, what replaces them? The study found a striking prevalence of white thread-like arterioles. These attenuated, ghost-like vessels were present in a remarkable 80.0% of eyes in Quartile 4, but were completely absent (0%) in Quartile 1.
When small vascular branches regress due to profound closure, the remaining arterioles attenuate into these distinct white lines, rendering the surrounding fundus unremarkable.
Fascinatingly, arteriolar sheathing was actually included as a marker of severe NPDR in the original Airlie House classification. However, it was dropped from the modified ETDRS classification because it lacked the easy reproducibility of red dot counting.
This study makes a strong argument for resurrecting arteriolar attenuation as a paramount clinical warning sign. In a retina devoid of hemorrhages, the presence of these thread-like vessels should instantly trigger suspicion of massive non-perfusion.
The Systemic Ischemic Phenotype: A Microvascular Triad
Perhaps the most clinically vital aspect of this research is the systemic profile of the patients who present with featureless retinas. The eyes in Quartile 4 did not exist in a vacuum; they belonged to patients suffering from a highly specific, advanced systemic ischemic phenotype.
Compared to patients in Quartile 1, those in Quartile 4 were generally older and overwhelmingly had Type 2 diabetes (88.0% vs. 64.0%).
However, their duration of diabetes and HbA1c levels did not significantly differ from the milder ischemia group.
The authors suggest that this could indicate a long, insidious, and subclinical phase of undiagnosed Type 2 diabetes in these patients.
More importantly, the degree of retinal ischemia strongly mirrored the degree of systemic microvascular collapse. Patients in Quartile 4 had dramatically higher rates of severe systemic complications:
- Renal Failure: 36.0% in Quartile 4 vs. 8.0% in Quartile 1. Crucially, 20.0% of the highly ischemic group required dialysis or a kidney transplant, compared to 0% in the mild group.
- Peripheral Neuropathy: 56.0% vs. 28.0%.
- Peripheral Artery Disease (PAD): 36.0% vs. 8.0%.
- Limb Amputation/Revascularization: 28.0% vs. 4.0%.
Notably, the study found no significant differences in macrovascular complications like stroke or coronary heart disease between the quartiles. This points toward a specific vulnerability in the small, distal microvasculature.
In diabetes, PAD frequently involves infrapopliteal arteries and features a heavy microvascular component that impairs collateral vessel formation, driving critical limb ischemia.
The data suggests a shared pathophysiological mechanism linking the capillary beds of the retina, the glomeruli of the kidneys, and the distal extremities.
Therefore, severe retinal non-perfusion is not just an ocular finding; it is a direct window into systemic microvascular end-stage failure.
Limitations and Future Directions
While the findings are robust, the authors note a few limitations that warrant consideration. The retrospective design and sample size of 100 eyes mean the results should be generalized with care. The NPI was manually delineated, which, while highly reproducible (ICC of 0.92), is subjective and time-consuming, particularly in the far periphery where UWF distortion occurs. Furthermore, the study relied on a single central UWF image without peripheral steering, which might underestimate the true extent of peripheral capillary non-perfusion. Finally, the study did not specifically quantify macular ischemia, which can occasionally progress independently of peripheral non-perfusion. Future studies utilizing automated AI-driven NPI quantification and specific macular OCTA analysis will be highly valuable in expanding upon this framework.
Clinical Translation for the Retina Specialist
The “featureless retina” presents a formidable diagnostic challenge. When we evaluate a patient with diabetes, we are mentally wired to tally up microaneurysms, blot hemorrhages, and venous beading to calculate ETDRS severity. If the fundus looks relatively “quiet,” the natural reflex is to grade the retinopathy as mild to moderate NPDR and schedule a routine follow-up.
This study demands a paradigm shift in how we approach specific high-risk cohorts. Absence of evidence is not evidence of absence. Extensive capillary closure can obliterate the very lesions we use to diagnose the disease.
To avoid underdiagnosing severe PDR in highly ischemic eyes, retina specialists should adopt the following clinical heuristics:
- Look Past the Red: If the retina lacks hemorrhages and microaneurysms, actively search for white thread-like arterioles. If these attenuated vessels are present, you must assume severe capillary non-perfusion until proven otherwise.
- Examine the Fellow Eye: In this study, 92.0% of patients in the highest ischemic quartile had established PDR in their contralateral eye. A quiet retina in one eye paired with severe PDR in the other is a massive red flag.
- Treat the Whole Patient, Not Just the Eye: Before grading the fundus photo, review the patient’s systemic history. If a patient with long-standing Type 2 diabetes has a history of end-stage renal disease (especially dialysis), peripheral neuropathy, diabetic foot ulcers, or a history of lower-limb amputation, their risk of having a “featureless” highly ischemic retina is exceptionally high.
- Lower the Threshold for Angiography: In patients exhibiting the systemic triad of neuropathy, nephropathy, and PAD, or those showing thread-like arterioles on CFP, standard color imaging is insufficient. Wide-field fluorescein angiography (or wide-field OCTA) should be strongly considered to unmask hidden neovascularization and map the true extent of the non-perfusion.
By understanding the paradoxical nature of the featureless retina, we can prevent severe, vision-threatening complications from hiding in plain sight.
🩺 High-Yield Board Exam Tips: Featureless Diabetic Retinopathy
- The “Featureless Retina” Paradox: In cases of proliferative diabetic retinopathy (PDR), eyes with the most severe retinal non-perfusion (ischemia) can paradoxically show significantly fewer retinal lesions on ultra-wide field fundus photography. This presentation includes a notable reduction in visible microaneurysms, intraretinal hemorrhages, cotton-wool spots, and intraretinal microvascular abnormalities (IRMAs).
- The Key Physical Exam Clue: Watch out for white thread-like arterioles on the fundus exam. These are heavily associated with advanced arteriolar obliteration and were found in 80% of eyes with the highest non-perfusion index, compared to being completely absent in low-ischemia eyes.
- High-Risk Systemic Associations: You should strongly suspect this hidden, severe retinal ischemia in patients who present with other advanced systemic microangiopathies and macroangiopathies. The highest ischemic risk is strongly linked to long-standing type 2 diabetes complicated by end-stage kidney disease (often requiring dialysis or transplant), severe peripheral neuropathy, and peripheral arterial disease (PAD) that has resulted in lower-extremity amputations or revascularization.
- Diagnostic Next Steps: Because extensive capillary closure can effectively obliterate classic hallmark lesions, disease severity can be vastly underestimated if you rely solely on color fundus photography. When highly ischemic PDR is suspected—especially in high-risk patients showing white thread-like arterioles or severe systemic complications—the next best step is to order a fluorescein angiography to reveal the true extent of the non-perfusion and underlying neovascularization.
Reference: Torres-Villaros, H., Lachiver, L., Fajnkuchen, F., Morel, J.-B., Arsalane, M., & Giocanti-Aurégan, A. (n.d.). Severe retinal non-perfusion is associated with fewer retinal lesions on ultra-wide field fundus photography in proliferative diabetic retinopathy. Retina. DOI: 10.1097/IAE.0000000000004912


