
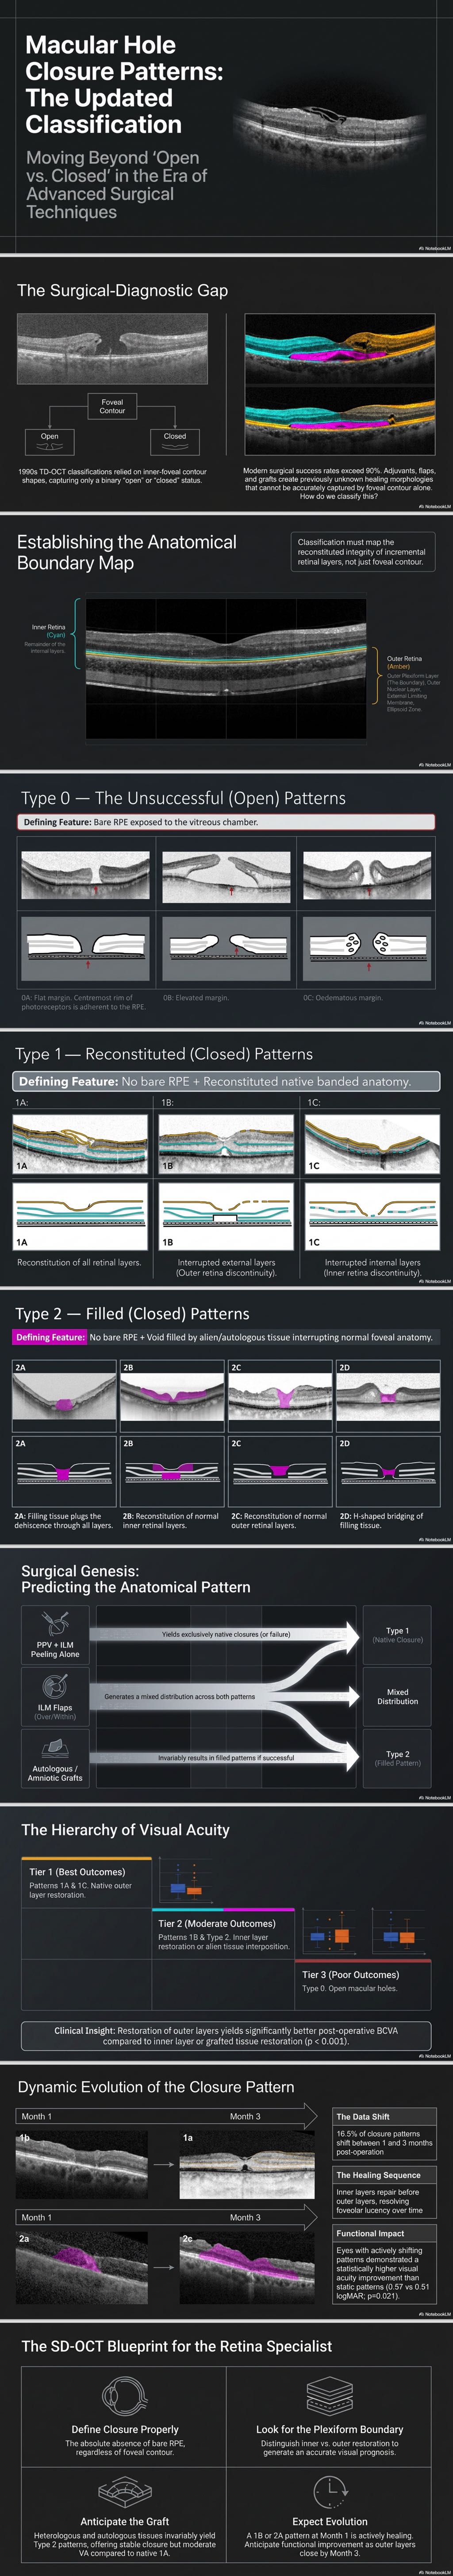
Since the advent of pars plana vitrectomy (PPV) for macular holes (MH) by Kelly and Wendel in 1991, which initially yielded a 58% closure rate, the surgical landscape has evolved dramatically. Today, anatomical success rates frequently exceed 90%, driven by the integration of internal limiting membrane (ILM) peeling, inverted ILM flap techniques, subretinal fluid injection, and the use of adjuvants like human amniotic membrane and autologous retinal grafts. However, despite these remarkable anatomical achievements, functional improvement remains highly variable and, at times, difficult to predict.
As surgical techniques have become more sophisticated, they have generated novel postoperative healing morphologies that challenge our traditional understanding of a “closed” macular hole. For years, retina specialists have relied on time-domain optical coherence tomography (TD-OCT) classifications, such as the pioneering binary system by Kang and colleagues that simply categorized holes as “open” or “closed,” or the morphological U-, V-, and W-shaped contours proposed by Imai and colleagues in 1999. These older paradigms focused almost exclusively on the inner foveal contour and the presence or absence of a neurosensory defect, failing to account for the crucial restoration of individual retinal layers.
To address this gap, an updated, spectral domain OCT (SD-OCT)-based classification system has been proposed by Rossi et al., aiming to encompass the entire spectrum of macular hole closure patterns (MHCPs) generated by modern surgical techniques. This comprehensive guide explores this new classification, its correlation with surgical techniques, and its profound implications for predicting visual outcomes.
The Paradigm Shift: From Foveal Contour to Retinal Layer Reconstitution
The fundamental principle of the updated classification system relies on evaluating the reconstituted integrity of an incremental proportion of restored retinal layers visible on postoperative SD-OCT, rather than merely assessing the inner foveal profile. Importantly, the classification redefines “MH closure” as a state where no bare retinal pigmented epithelium (RPE) is exposed to the vitreous chamber, and there is tissue continuity over the RPE. This continuity can be achieved either by normal-looking retina with reconstituted anatomy or by autologous/heterologous filling tissue plugging the void.
To establish clear anatomical boundaries for the classification, the authors defined the “outer retina” as comprising the ellipsoid zone, the external limiting membrane (ELM), the outer nuclear layer (ONL), and the outer plexiform layer (OPL). The OPL essentially marks the definitive boundary separating the outer structures from the “inner retina,” which includes the remainder of the overlying retinal layers.
The Updated Classification Framework
Based on a retrospective review of 253 eyes (encompassing idiopathic, chronic, myopic, and recurrent macular holes) evaluated by masked senior retina specialists, the new classification stratifies postoperative anatomy into three distinct types: Type 0, Type 1, and Type 2.
Type 0: Unsuccessful “Open” Macular Holes
Type 0 patterns represent surgical failures where bare RPE remains exposed to the vitreous chamber. Even if the hole rim is flat, the lack of tissue coverage over the central RPE mandates a non-closure designation.
- 0A: Open MH with a flat margin, where the centremost rim of photoreceptors is adherent to the underlying RPE.
- 0B: Open MH characterized by an elevated hole margin.
- 0C: Open MH characterized by an edematous margin.
Type 1: Closed Macular Holes with Native Reconstitution
Type 1 patterns denote successful closure utilizing the patient’s native local retinal tissue, demonstrating variable degrees of banded anatomical reconstitution.
- 1A: Reconstitution of all retinal layers. This represents the most anatomically optimal healing pattern.
- 1B: Reconstitution of the inner retina, but with a residual interruption of the external layers.
- 1C: Reconstitution of the outer retina, but with a residual interruption of the internal layers.
Type 2: Closed Macular Holes with Interposed “Filling” Tissue
Type 2 patterns are a direct consequence of modern adjunctive surgical techniques. In these cases, the MH is formally closed (no bare RPE exposed), but there is autologous or heterologous filling tissue (such as an ILM flap, human amniotic membrane, or autologous retinal graft) interrupting the normal foveal layered anatomy.
- 2A: The filling tissue heavily plugs the foveolar dehiscence, extending throughout all retinal layers.
- 2B: The filling tissue is present, but there is an observable reconstitution of normal inner retinal layers.
- 2C: The filling tissue is present, but there is an observable reconstitution of normal outer retinal layers beneath or adjacent to it.
- 2D: A rare morphology characterized by an “H-shaped” bridge of persistent filling tissue suspended between the hole edges.
| Closure Pattern Type | Anatomic Description | Retinal Layer Restoration Status | Associated Surgical Techniques | Post-operative BCVA (logMAR) | Closure Stability (Months 1-3) |
|---|---|---|---|---|---|
| Type 1A | Closed MH with reconstitution of the banded anatomy throughout all retinal layers. | Full restoration of all retinal layers (inner and outer). | ILM peeling, ILM flap over or within MH | 0.38 | Stable (often the final stage of evolution from 1B) |
| Type 1B | Closed MH with residual interruption of the external retinal layers. | Internal layers restored; external layers (ellipsoid zone, ELM, etc.) interrupted. | ILM peeling, ILM flap, Autologous retinal transplant | 0.48 | Highly evolving (frequently becomes 1A) |
| Type 1C | Closed MH with residual interruption of the internal retinal layers. | External layers restored; internal layers interrupted. | ILM peeling, ILM flap | 0.33 | Stable |
| Type 2A | Closed MH with filling tissue (plugs) through all layers interrupting foveal anatomy. | Layers interrupted by filling tissue throughout. | ILM flap within MH, Amniotic membrane patch, Autologous retinal transplant | 0.79 | Evolving (frequently becomes 2C) |
| Type 2B | Closed MH with filling tissue and reconstitution of normal inner retinal layers. | Inner layers restored; filling tissue present in outer layers. | ILM flap, Amniotic membrane patch, Autologous retinal transplant | 0.74 | Evolving |
| Type 2C | Closed MH with filling tissue and reconstitution of normal outer retinal layers. | Outer layers restored; filling tissue present in inner layers. | ILM flap, Amniotic membrane patch, Autologous retinal transplant | 1.12 | Stable (often result of evolution from 2A) |
| Type 2D | Closed MH with H-shaped bridging of filling tissue. | Filling tissue forms a bridge; layers interrupted. | ILM flap, Autologous retinal transplant | 0.72 | Evolving |
| Type 0A | Open MH with centremost rim of photoreceptors adherent to the RPE (flat margin). | No restoration; bare retinal pigmented epithelium (RPE) exposed to vitreous. | ILM peeling, ILM flap (failed cases) | 1.30 | Stable |
| Type 0B | Open MH with elevated centremost rim of photoreceptors. | No restoration; bare RPE exposed to vitreous. | ILM peeling, ILM flap, Autologous retinal transplant (failed cases) | 1.35 | Evolving (one case changed between months 1 and 3) |
| Type 0C | Open MH with oedematous centremost rim of photoreceptors. | No restoration; bare RPE exposed to vitreous. | ILM peeling, ILM flap (failed cases) | 0.85 | Stable |
The Correlation Between Surgical Technique and Closure Pattern
The study analyzed outcomes across five distinct surgical approaches: (1) PPV with ILM peeling alone, (2) ILM inverted flap placed over the MH, (3) ILM inverted flap placed within the MH, (4) human amniotic membrane implants, and (5) autologous retinal transplants. The type of surgery utilized significantly and directly influenced the resulting closure pattern (p < 0.001).
Notably, traditional PPV with ILM peeling tout court strictly resulted in Type 1 closures (unless the surgery failed, resulting in Type 0). The application of an ILM flap over or within the hole resulted in a highly heterogeneous mix of closure types. Conversely, the employment of grafted tissues—specifically human amniotic membrane and autologous retinal transplants—invariably resulted in Type 2 closure patterns if anatomically successful. Interestingly, the choice of gas or oil tamponade showed no significant correlation with either the overall closure rate or the specific healing pattern achieved.
Visual Outcomes: Anatomy Dictates Function
The overarching closure rate in the analyzed cohort was an impressive 95.2%. However, the most vital insight from this classification system is its strong prognostic value regarding best-corrected visual acuity (BCVA).
Postoperative BCVA was significantly different among the closure patterns (p < 0.001). When clustered by primary types, Type 1 closures (native reconstitution) achieved significantly superior visual acuities compared to Type 2 closures (filling tissue), which in turn performed significantly better than Type 0 (open) cases.
A deeper analysis based on specific layer integrity revealed that Type 1A and Type 1C patterns performed significantly better than all other morphological outcomes. The restoration of the outer retinal layers (comprising patterns 1A, 1C, and 2C) proved to be the strongest predictor of excellent visual recovery. Patients achieving outer layer restoration saw visual acuities of 0.63 ± 0.26 logMAR at 1 month and 0.35 ± 0.21 logMAR at 3 months, which was significantly superior to those who only achieved inner retinal layer restoration (types 1B and 2B), who saw 0.82 ± 0.27 and 0.68 ± 0.24 logMAR respectively (p < 0.001).
Furthermore, while the interposition of grafted “alien” tissue (Type 2A, 2D) yielded significantly better visual acuity than an open hole, it predictably resulted in worse functional outcomes compared to cases where native outer or inner retinal restoration was achieved.
The Dynamics of Healing: Shifting Patterns Over Time
Macular hole healing is not a static binary event but a dynamic, evolving biological process. The SD-OCT classification system provides a unique window into these temporal shifts. In the study, 16.5% of eyes demonstrated a change in their macular hole closure pattern between the 1-month and 3-month postoperative visits.
Crucially, eyes that exhibited a shifting closure pattern experienced a significantly higher visual acuity improvement between month 1 and month 3 compared to eyes whose patterns remained static (-0.19 ± 0.29 vs -0.08 ± 0.21 logMAR; p = 0.018).
The most frequently observed anatomical shifts provide a roadmap of macular healing:
- Type 1B shifting to Type 1A (28.6% of shifts): This demonstrates that the inner retinal layers tend to repair and approximate before the outer layers. This delayed outer retinal repair corresponds to the classic finding of “foveolar lucency,” an optical phenomenon historically associated with higher ultimate closure rates and gradual photoreceptor recovery.
- Type 2A shifting to Type 2C (19.1% of shifts): In cases utilizing grafts, the initial dense plug spanning all layers (2A) often evolves as the outer retina reconstitutes beneath or alongside it (2C). This is likely facilitated by the graft acting as a scaffold for tissue guidance, localized pooling of growth factors, or the shifting of adjacent glial tissue.
Even in complex cases requiring autologous retinal transplants, continuous morphological evolution is evident. An initial Type 2A presentation immediately post-op often becomes fainter by month 3, and can sometimes completely disappear by 19 months, eventually mimicking a Type 1B pattern with only a small ellipsoid zone defect remaining.
Conclusion
As retina specialists continue to push the boundaries of surgical intervention for complex, large, myopic, and recurrent macular holes, our descriptive language must evolve in tandem. The “open versus closed” binary is obsolete. A morphology-based classification system rooted in SD-OCT findings—which accounts for the specific reconstitution of the outer plexiform, outer nuclear, and ellipsoid zones, alongside the presence of grafted tissues—offers a far more accurate representation of surgical reality. By adopting this updated terminology, clinicians can better standardize the assessment of postoperative anatomy, improve their understanding of complex healing mechanisms, and most importantly, provide patients with more accurate visual prognoses.
References
Rossi, T., Bacherini, D., Caporossi, T., Telani, S., Iannetta, D., Rizzo, S., Moysidis, S. N., Koulisis, N., Mahmoud, T. H., & Ripandelli, G. (2020). Macular hole closure patterns: an updated classification. Graefe’s Archive for Clinical and Experimental Ophthalmology. https://doi.org/10.1007/s00417-020-04920-4.


