
For decades, retina specialists have relied on fundus autofluorescence (FAF) as a window into the metabolic health of the retinal pigment epithelium (RPE). By capturing the intrinsic fluorescence of lipofuscin and other fluorophores, FAF has provided invaluable qualitative insights into diseases like age-related macular degeneration (AMD). However, the transition from “bright vs. dark” to “how much” has been hindered by technical variability—until the advent of Quantitative Fundus Autofluorescence (QAF).
This post explores the technical foundations, clinical applications, and future potential of QAF as a biomarker for RPE health, specifically in the context of AMD.
The Technical Leap: Beyond Qualitative Interpretation
The primary limitation of traditional FAF is its lack of a standardized scale. Signal intensity depends heavily on laser power, detector gain, and media opacities, making longitudinal or multicenter comparisons difficult.
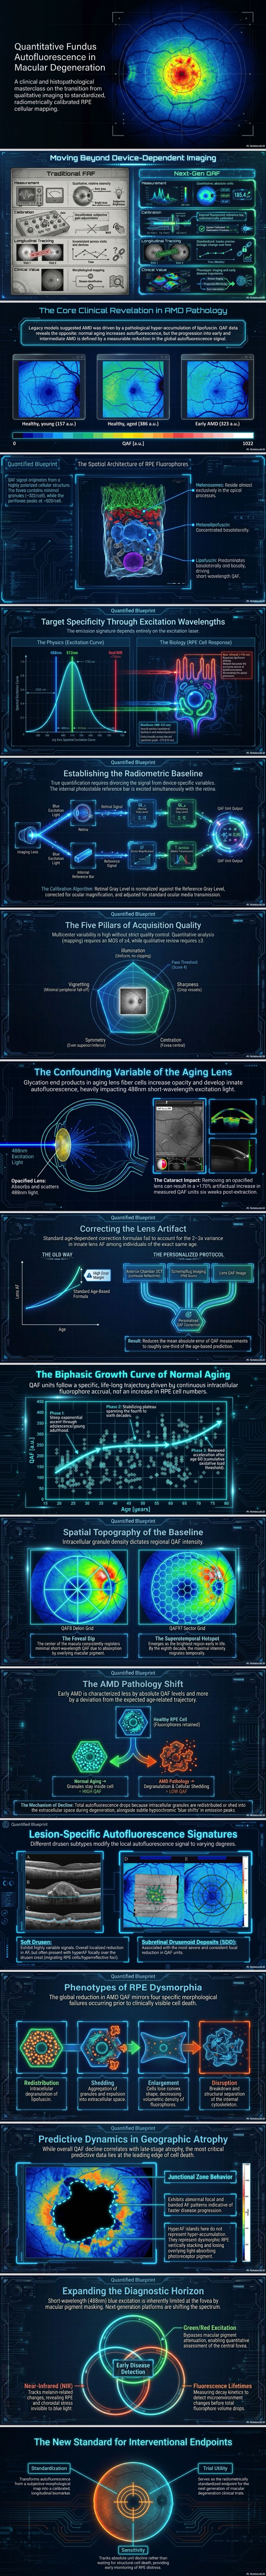
QAF overcomes this through an internal reference bar placed within the optical path of the confocal scanning laser ophthalmoscope (cSLO). This reference is excited simultaneously with the retina, allowing for the normalization of the autofluorescence signal. The resulting QAF value is calculated based on the mean gray level of the retinal region relative to the reference, adjusted for instrument calibration, ocular magnification, and media transmission.
Optimizing Image Acquisition
For the retina specialist, obtaining high-quality QAF is an active process. A standard protocol includes:
- Pharmacologic dilation: Mandatory for accurate signal capture.
- Bleaching: A minimum of 30 seconds of exposure to excitation light is required to bleach visual pigments (rhodopsin/cone pigments) that would otherwise absorb the 488 nm light and falsely lower QAF values.
- Quality Grading: The use of a 5-point Mean-Opinion-Score (MOS) is recommended to evaluate focus, centration, and illumination uniformity. Images for quantitative analysis should ideally reach a MOS of ≥4.
The “Lens Problem”: Addressing Media Opacity
One of the most significant challenges in QAF imaging, particularly in an aging AMD population, is the crystalline lens. The short-wavelength blue light (488 nm) used in QAF is highly susceptible to absorption and scattering by age-related lens opacities.
Research has shown that QAF units can increase by more than 170% following cataract extraction. While standard age-based correction formulas exist, they often fail to account for individual variability in lens fluorescence and density. Recent advancements suggest a personalized correction approach using Scheimpflug imaging and anterior-chamber OCT to measure innate lens AF and opacification. This personalized approach has been shown to reduce the mean absolute error of QAF measurements by nearly two-thirds compared to age-based models.
QAF in the Normal Aging Retina
To understand AMD, we must first understand the healthy aging trajectory. QAF reveals a biphasic, non-linear growth curve of RPE fluorophores throughout life.
- Youth to Middle Age: There is a rapid surge in QAF during adolescence, followed by a plateau through the fourth to sixth decades.
- The Over-60 Surge: After age 60, QAF values begin to rise again at a rate similar to early adulthood.
- Spatial Patterns: The superotemporal crescent is typically the brightest region in healthy eyes, while the fovea remains a relative minimum due to the absorption of excitation light by macular pigment.
The AMD Paradox: Why “More” Isn’t Always the Case
Historically, AMD was thought to be driven by the pathological accumulation of lipofuscin. However, QAF studies have largely debunked this “excessive lipofuscin” theory.
Independent studies consistently show that QAF is normal or significantly reduced in AMD compared to age-matched controls.
- Intermediate AMD: Shows a marked decrease in QAF units, particularly in the presence of subretinal drusenoid deposits (SDD).
- Geographic Atrophy (GA): GA represents the nadir of QAF, with pronounced signal loss in atrophic areas. Interestingly, while the junctional zone of GA may show “hyperAF” on traditional FAF, QAF studies often reveal that these areas still possess reduced or normal AF levels compared to healthy tissue, suggesting the “brightness” may be due to structural alterations and loss of light-absorbing pigments rather than lipofuscin buildup.
Cellular and Histological Correlates
What explains this reduction in QAF on a cellular level? Advanced imaging techniques like serial block-face scanning electron microscopy (SBFSEM) and structured illumination microscopy (SIM) have provided the answers.
In AMD-affected eyes, RPE cells undergo profound dysmorphia:
- Granule Redistribution: Lipofuscin and melanolipofuscin granules aggregate and are redistributed.
- Degranulation and Shedding: Cells lose their granule content through shedding into the extracellular space.
- Morphological Transformation: RPE cells lose their regular polygonal shape, becoming larger, irregular, or concave.
- Cytoskeletal Stress: These changes are often accompanied by disruptions in the cell’s cytoskeleton.
These findings suggest that reduced QAF is a direct reflection of RPE distress and granule loss, rather than just a lack of accumulation.
Clinical Utility and Longitudinal Monitoring
QAF is emerging as a potent tool for monitoring disease progression. Longitudinal data suggests that a progressive decline in QAF over time may serve as an early indicator of impending RPE atrophy.
- Progression Risk: In one study, a stronger decline in QAF was associated with a significantly higher hazard ratio for developing late-stage GA.
- Lesion-Specific Analysis: New software tools (like the QAF97 grid) allow specialists to analyze QAF in specific regions, such as the areas immediately surrounding drusen or the transition zones of GA.
The Future: Multimodal and Multi-Wavelength AF
The field is moving toward a more nuanced assessment of RPE health through several emerging technologies:
- Alternative Excitation Wavelengths:
- Green-AF (≈512–532 nm): Reduces interference from macular pigment, allowing for better foveal quantification.
- Near-Infrared AF (NIR-AF, >780 nm): Targets melanin rather than lipofuscin, providing insights into different RPE and choroidal changes.
- Fluorescence Lifetimes (FLIO): Measuring how long fluorophores remain in an excited state can detect metabolic changes before structural loss occurs.
- AI Integration: Deep learning algorithms are already being implemented to automate image quality assessment and predict retest reliability, making QAF more viable for large-scale clinical trials.
Conclusion
For the retina specialist, QAF represents a significant advancement in our ability to quantify the “metabolic clock” of the RPE. While traditional FAF provided a snapshot of disease, QAF provides a calibrated measurement that can track the gradual decline of RPE health in AMD. By understanding that AMD is characterized by a loss of AF signal and cellular dysmorphia, we can better identify patients at high risk for atrophy and, eventually, monitor the efficacy of emerging RPE-protective therapies.
Reference
von der Emde L, Reiter GS, Mallwitz M, et al. Quantitative fundus autofluorescence in age-related macular degeneration. Survey of Ophthalmology. 2026. doi:10.1016/j.survophthal.2026.03.018.


