
The clinical management of proliferative diabetic retinopathy (PDR) is currently undergoing a paradigm shift, moving from reactive treatments like panretinal photocoagulation (PRP) to proactive, individualized risk stratification enabled by advanced imaging and molecular biomarkers. While traditional classifications have long guided our threshold for intervention, a deeper understanding of the pathobiological framework and the “real-world” challenges of treatment adherence necessitates a more nuanced approach for the modern retina specialist. This post explores the current landscape of PDR progression, the emerging “biomarker blueprint,” and the future of disease-modifying therapies.
The Pathobiological Framework: From Metabolic Insult to Angiogenesis
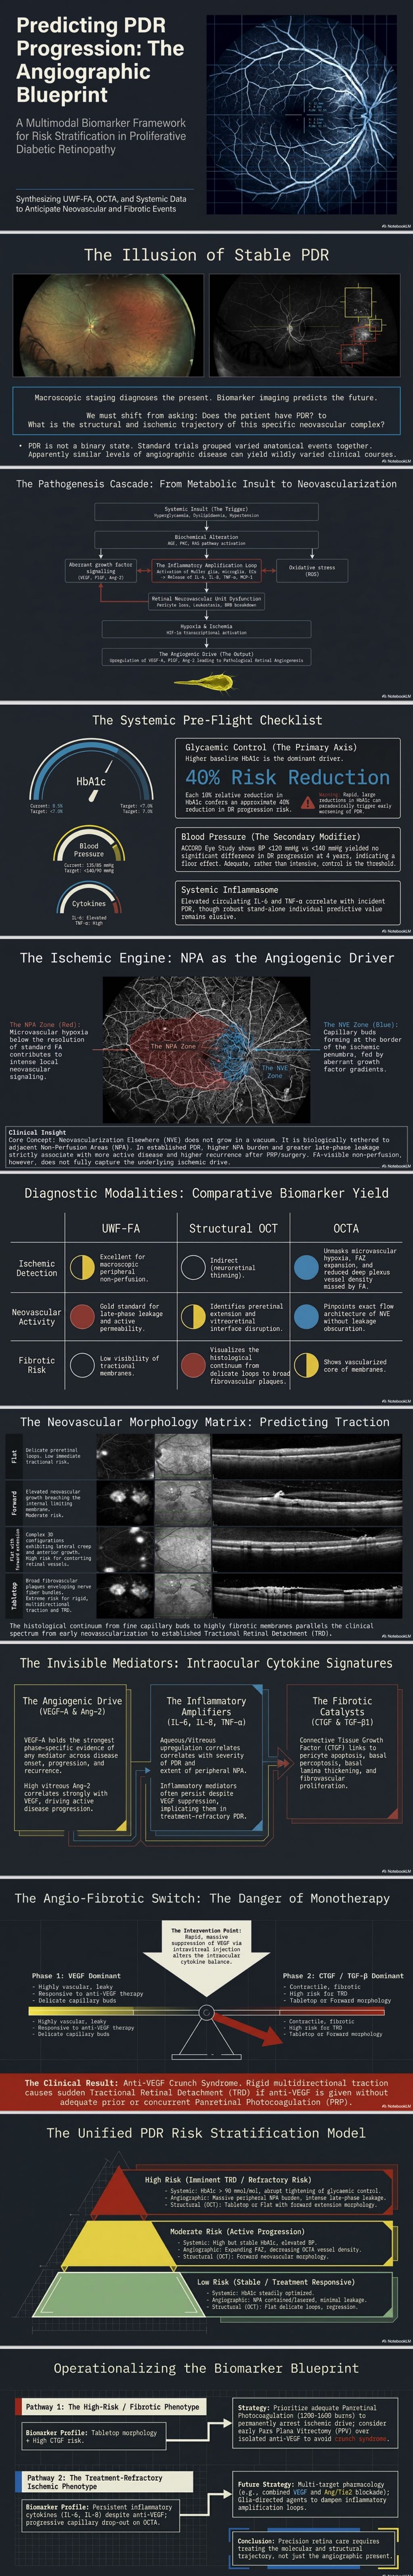
The transition to PDR is not a sudden event but the culmination of a complex, multi-stage cascade. It begins with chronic metabolic insults—hyperglycemia, dyslipidemia, and hypertension—which alter biochemical pathways including the polyol, hexosamine, and protein kinase C (PKC) pathways. These alterations activate resident retinal cells, such as Müller glia and microglia, leading to the release of inflammatory cytokines like IL-6, IL-8, and TNF-α.
This inflammatory milieu induces oxidative stress and retinal neurovascular unit (NVU) dysfunction, characterized by pericyte loss, basement membrane thickening, and blood-retinal barrier (BRB) breakdown. The resulting microvascular hypoxia triggers the upregulation of potent growth factors, most notably vascular endothelial growth factor (VEGF), placental growth factor (PlGF), and angiopoietin-2 (Ang-2). Among these, VEGF-A 165a remains the strongest phase-specific driver of pathological angiogenesis in PDR. The delicate balance between diffusible VEGF isoforms and those tethered to the extracellular matrix (ECM) dictates the morphology of sprouting vessels and their susceptibility to traction.
Advanced Imaging Biomarkers: Stratifying the “At-Risk” Eye
Standard color fundus photography and the modified Airlie House classification remain foundational, but ultra-widefield (UWF) imaging and optical coherence tomography (OCT) have revolutionized our ability to detect “clinically occult” high-risk disease.
- UWF Fluorescein Angiography (UWF-FA): The retinal non-perfusion area (NPA) is a primary predictor of progression. Extensive late-phase leakage on FA is associated with more active disease and higher rates of recurrence following treatment. Interestingly, some eyes exhibit neovascularization of the elsewhere (NVE) without significant FA-visible non-perfusion, suggesting that microvascular hypoxia below the resolution of current FA may still drive pro-angiogenic signaling.
- Structural OCT and OCT Angiography (OCTA): Structural OCT allows for the classification of neovascular morphology into “flat,” “forward,” “flat with forward extension,” and “tabletop” configurations. These 3-dimensional configurations reflect the histological continuum from fine capillary loops to broad fibrovascular plaques, which translate clinically into rigid, multidirectional traction. On OCTA, reduced superficial and deep plexus vessel density, along with enlarged foveal avascular zone (FAZ) metrics, correlate with disease severity, although quantitative clinical cutoffs are still being refined.
- The Predictive Value of PPLs: Predominantly peripheral lesions (PPLs) on UWF imaging have been identified as a key imaging biomarker, often signaling a higher risk of progression to PDR from earlier stages.
Systemic Drivers: The Retinal-Renal Link and Glycemic Paradoxes
Retina specialists must look beyond the eye to manage the systemic modifiers of PDR progression.
- Hemoglobin A1c (HbA1c): As the primary biomarker of chronic glycemic exposure, HbA1c is a robust predictor of progression. Every 10% relative reduction in HbA1c is associated with an approximate 40% reduction in DR progression risk. However, clinicians must be wary of the “early worsening” phenomenon; rapid, intensive improvements in HbA1c can paradoxically accelerate PDR onset in patients with long-standing poor control.
- Hypertension and Dyslipidemia: While hypertension is a critical modifier, some trials, like the ACCORD Eye Study, suggest a “floor effect” where intensive blood pressure control (<120 mmHg) offers no additional retinal benefit over standard control (<140 mmHg). Dyslipidemia remains a weaker independent predictor compared to glycemia.
- The Retinal-Renal Axis: The microcirculations of the retina and kidney share striking structural and pathogenic similarities. The presence of nephropathy, albuminuria, and elevated creatinine levels mirrors retinal disease progression, with albuminuria reflecting systemic microvascular endothelial dysfunction.
The Molecular Soup: Intraocular and Systemic Biomarkers
While imaging is the current clinical standard, the “molecular soup” within the vitreous and aqueous provides critical mechanistic insights.
- Pro-angiogenic and Inflammatory Cytokines: Elevated levels of VEGF, PlGF, IL-6, and MCP-1 in ocular fluids correlate with the extent of peripheral NPA and disease activity.
- The Role of Fibrosis: Connective tissue growth factor (CTGF) and TGF-β1 are implicated in the “angio-fibrotic switch,” where neovascular loops evolve into traction-prone fibrovascular membranes. Serum TGF-β1 levels have been reported to reflect both disease severity and response to anti-VEGF therapy.
- Current Limitations: Most biomarker data are currently cross-sectional or based on small longitudinal series. Robust data demonstrating that these markers add predictive value over conventional imaging are still lacking.
Real-World Challenges: Progression Despite Treatment
A significant challenge in PDR management is distinguishing true biological progression from progression due to “inadequate” treatment.
- PRP and Anti-VEGF: While PRP remains a foundational therapy that reduces the risk of severe vision loss by 50%, the exact “dose” required to arrest angiogenic drive varies by patient. Anti-VEGF therapy offers excellent regression of neovascularization, but it carries the risk of “crunch syndrome”—the rapid contraction of fibrovascular tissue leading to tractional retinal detachment (TRD).
- Adherence and Socioeconomics: Factors such as younger age and socioeconomic disadvantage are significantly associated with loss to follow-up and worse outcomes, particularly in eyes treated with anti-VEGF monotherapy.
- Recurrent Vitreous Hemorrhage (VH): VH can arise from active bleeding or mechanical traction. Risk factors for recurrence after vitrectomy include extensive preoperative ischemia, younger age, and the presence of preoperative neovascular glaucoma.
Future Frontiers: Regeneration and Multi-Target Pharmacology
The next decade of PDR management will likely focus on “disease modification” rather than just symptom control.
- Restorative Vascular Therapies: Emerging strategies aim to reperfuse non-perfused retina or promote physiological revascularization using endothelial-targeted cell or gene therapies.
- Neuroprotection: Interventions targeting retinal neurons and glia could dampen inflammatory loops and improve the retina’s resilience to ischemic stress.
- Multi-target Pharmacology: Combined blockade of VEGF with pathways like Ang/Tie2 or pro-fibrotic mediators (e.g., CTGF) may address both the angiogenic and fibrotic arms of PDR, preventing the angio-fibrotic “switch”.
- Regenerative Approaches: Cell-based therapies, including the transplantation of endothelial or pericyte progenitors, represent a future paradigm for replenishing damaged components of the neurovascular unit.
Conclusion
For the retina specialist, effective PDR management now requires an integrated approach that combines high-resolution imaging with a deep understanding of systemic and molecular risk factors. By identifying high-risk phenotypes early and addressing the systemic drivers of disease, we can move closer to the goal of truly restorative and personalized care for our patients.
Reference: Brendan Luu et al., Progress and Risk Stratification in Proliferative Diabetic Retinopathy, Survey of Ophthalmology, 2026. https://doi.org/10.1016/j.survophthal.2026.06.009.


