
Macular telangiectasia type 2 (MacTel) is a bilateral retinal disease known for its high phenotypic variability, making it a frequent diagnostic challenge for retina specialists. With the recent emergence of potential therapeutic options, the need for an accurate diagnosis has never been more critical to ensure patients receive appropriate care and are correctly enrolled in clinical trials.
A recent large-scale study utilizing data from the MacTel Natural History Observation Registry (NHOR) has shed light on the most common “masquerading” diseases that clinicians often mistake for MacTel.
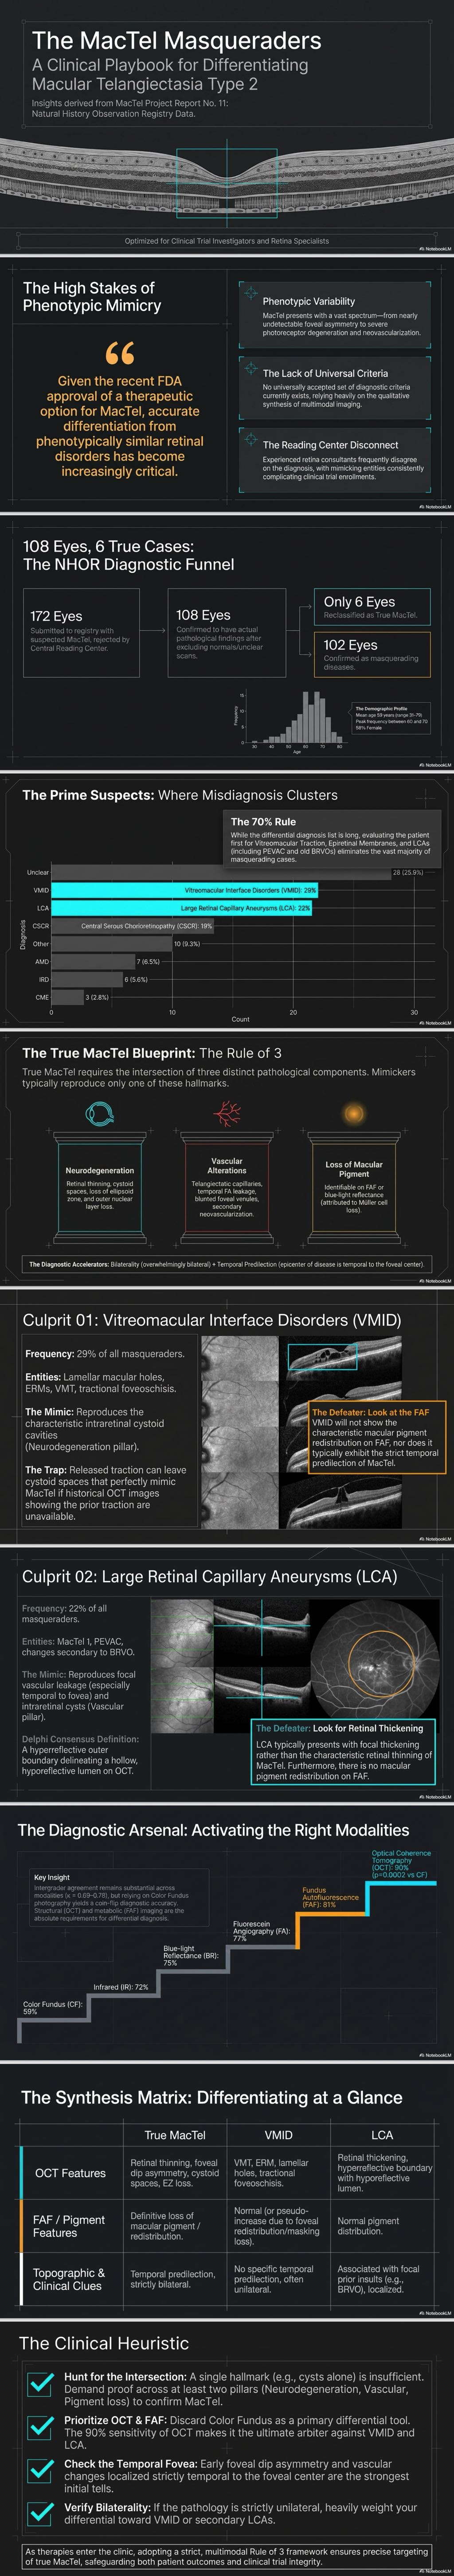
The “Big Three” Masqueraders
The study identified three primary clusters of diseases that most frequently mimic MacTel:
- Vitreomacular Interface Disorders (VMID) – 29%: This is the most common mimic, including conditions like epiretinal membranes, vitreomacular traction, and lamellar macular holes. These conditions often mimic the intraretinal cystoid spaces characteristic of MacTel.
- Large Retinal Capillary Aneurysms (LCA) – 22%: This group includes MacTel type 1 and Perifoveal Vascular Anomalous Complex (PEVAC). These often mimic the vascular leakage patterns of MacTel, particularly when located temporal to the fovea.
- Central Serous Chorioretinopathy (CSCR) – 19%: Characterized by subretinal fluid or RPE alterations, CSCR can present phenotypic overlaps that confuse the initial clinical picture.
Other less frequent mimics include age-related macular degeneration (7%), cystoid macular edema (7%), and various inherited retinal diseases (6%).
Choosing the Right Tools: The Power of Multimodal Imaging
The study evaluated several imaging modalities to determine which is most effective at unmasking these mimics. The results were clear: Optical Coherence Tomography (OCT) is the gold standard.
- OCT (90% sensitivity): Significantly outperformed traditional color fundus photography. It is essential for identifying retinal thinning (common in MacTel) versus retinal thickening (common in many mimics like LCA).
- Fundus Autofluorescence (FAF) (81% sensitivity): Highly effective because it can detect the loss of macular pigment, a hallmark of MacTel that is rarely seen in other diseases.
- Color Fundus Photography (59% sensitivity): Proved to be the least reliable method for differentiating MacTel from its mimics.
Clinical Pearls for Accurate Diagnosis
To avoid misdiagnosis, clinicians should look for a combination of these three MacTel hallmarks:
- Neurodegeneration: Retinal thinning and loss of the ellipsoid zone on OCT.
- Vascular Alterations: Telangiectatic capillaries or blunted venules.
- Macular Pigment Loss: Visible as increased signal on FAF or blue-light reflectance.
Furthermore, while many mimics are unilateral, MacTel is typically a bilateral disease. Checking the fellow eye can often provide the deciding clue in a challenging case.
Conclusion
Distinguishing MacTel from its mimics requires a move beyond simple fundus exams toward a comprehensive multimodal imaging approach. By prioritizing OCT and FAF, clinicians can achieve high diagnostic accuracy, ensuring that MacTel “masqueraders” are correctly identified and managed.
Reference Pauleikhoff L, Charbel Issa P, Heeren TFC, et al. Masquerading disease of macular telangiectasia type 2 – MacTel Project Report No 11. Ophthalmology Retina. [Date of Publication/Pre-proof]..


