
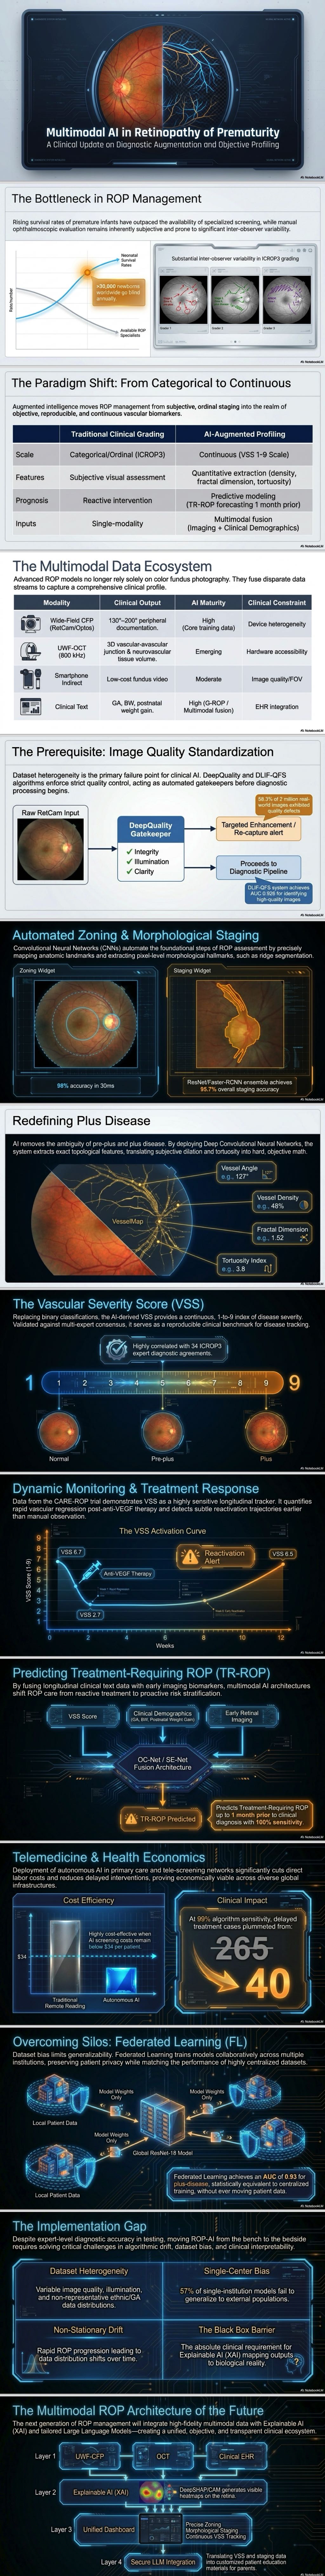
Retinopathy of prematurity (ROP) remains a leading cause of preventable childhood blindness globally, particularly as neonatal intensive care survival rates improve in low-resource regions. For the retina specialist and pediatric ophthalmologist, the traditional burden of ROP management—characterized by subjective ophthalmoscopic examinations, high inter-observer variability, and a shortage of trained specialists—is reaching a tipping point. However, recent breakthroughs in multimodal artificial intelligence (AI) are transforming ROP from a purely manual diagnostic challenge into a data-driven, precision medicine discipline.
Beyond the Fundus Image: The Rise of Multimodal Data
While wide-field color fundus photography (CFP) via devices like the RetCam remains the foundational dataset for AI training, we are moving toward a more holistic diagnostic approach. Modern AI models are now integrating diverse data streams, including:
- Ultra-Widefield (UWF) Imaging and FFA: New non-contact systems like the Optos 200Tx provide a 200° view, allowing AI to detect peripheral lesions more accurately than traditional systems.
- Optical Coherence Tomography (OCT): AI-driven OCT analysis offers a micron-level, 3D visualization of the vascular-avascular junction, introducing volumetric biomarkers like anomalous neurovascular tissue volume (ANVTV) that outperform traditional ordinal staging.
- Clinical Text and Demographic Data: By incorporating birth weight (BW), gestational age (GA), and longitudinal weight gain (as seen in the G-ROP study), models have achieved 100% sensitivity in predicting treatment-requiring ROP (TR-ROP), potentially reducing unnecessary exams by over 30%.
Standardizing Severity: The Vascular Severity Score (VSS)
One of the most clinically impactful developments is the Vascular Severity Score (VSS). Traditional “plus disease” diagnosis is often inconsistent among experts. AI-generated VSS provides a continuous 1–9 scale that serves as an objective benchmark for vascular tortuosity and dilation. Studies have shown that VSS not only improves inter-observer agreement but also serves as a sensitive tool for monitoring treatment response—dropping sharply after anti-VEGF therapy and rising during reactivation.
Telemedicine and Global Equity
The “bench-to-bedside” transition is most visible in telemedicine. AI algorithms validated in multi-country projects (e.g., Nepal, Mongolia, and India) have maintained an AUC above 0.96 for detecting plus disease, even when using low-cost smartphone-based indirect ophthalmoscopy. From an economic perspective, autonomous AI screening has proven more cost-effective than traditional remote reading in large-scale cohorts, provided screening costs remain low.
The Road Ahead: Privacy and Transparency
Despite these gains, challenges such as data heterogeneity and “black-box” algorithms persist. To address these, two emerging technologies are key:
- Federated Learning (FL): This allows institutions to collaborate on AI training without sharing sensitive neonatal health information, maintaining patient privacy while achieving performance levels comparable to centralized datasets.
- Explainable AI (XAI): New frameworks are providing clinicians with heatmaps and interactive visual feedback, highlighting the specific vascular features that led to a “plus disease” or “Stage 3” diagnosis, thereby increasing clinician trust.
As we move forward, the integration of multi-center, multi-ethnic datasets will be essential to ensure these models are robust across different populations. For the frontline specialist, multimodal AI promises not to replace clinical judgment, but to augment it with standardized, scalable, and equitable tools for preserving infant vision.
Source: [i] Zhao X, Wu Z, Wu S, et al. Multimodal artificial intelligence in retinopathy of prematurity: A comprehensive narrative review. Survey of Ophthalmology. 2026. doi:10.1016/j.survophthal.2026.05.006.


