
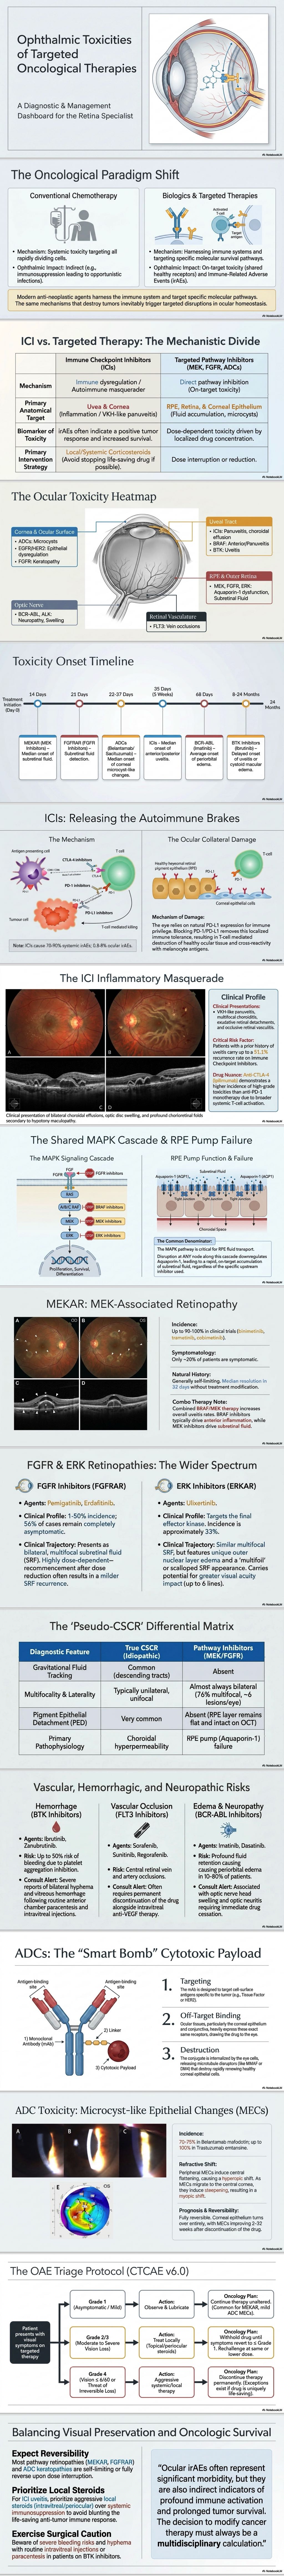
The landscape of oncology has been transformed by systemic immunotherapies and targeted therapies, significantly improving survival rates for various cancers. However, as these treatments expand, ophthalmic adverse events (OAEs)—particularly those affecting the retina and choroid—are increasingly recognized as vision-threatening complications that require vigilant management.
Standardizing Severity: The CTCAE Scale
Clinicians use the Common Terminology Criteria for Adverse Events (CTCAE v6.0) to grade these toxicities from Grade 1 (asymptomatic) to Grade 4 (severe, potential irreversible vision loss).
Retinal and Choroidal Manifestations by Drug Class
1. Immune Checkpoint Inhibitors (ICIs) While dry eye is the most common OAE, ICIs can trigger severe posterior segment inflammation by disrupting the eye’s immune privilege.
- Choroidopathy: ICIs can lead to Vogt-Koyanagi-Harada (VKH)-like panuveitis, multifocal choroiditis resembling Birdshot chorioretinopathy, and ciliochoroidal effusions.
- Retinopathy: Manifestations include exudative retinal detachments, autoimmune retinopathy, and melanoma-associated retinopathy.
- Vascular Issues: Patients may develop occlusive retinal vasculitis, Acute Macular Neuroretinopathy (AMN), or paracentral acute middle maculopathy due to bystander perivascular inflammation.
2. MAPK Pathway Inhibitors (MEK, BRAF, FGFR, and ERK) These agents target pathways essential for the health and fluid transport of the retinal pigment epithelium (RPE).
- MEKAR & FGFRAR: MEK and FGFR inhibitors cause self-limiting bilateral neurosensory retinal detachments (often called “pseudo-CSCR”). Unlike central serous chorioretinopathy, these typically show no choroidal thickening or vascular leakage.
- ERK Inhibitors: These can cause similar retinopathy but with a unique multifoil or scalloped appearance of the subretinal fluid.
- BRAF Inhibitors: These are linked to papillitis with multifocal neurosensory detachments, ischemic retinal vasculitis, and multifocal choroiditis with secondary choroidal neovascularization.
3. BTK and FLT3 Inhibitors These therapies can lead to significant fluid accumulation and bleeding in the posterior segment.
- BTK Inhibitors (e.g., Ibrutinib): Associated with posterior or panuveitis and refractory Cystoid Macular Edema (CMO). They also increase the risk of vitreous hemorrhage due to platelet dysfunction.
- FLT3 Inhibitors (e.g., Sunitinib): Linked to retinal arterial or venous occlusions, CMO, and VKH-like disease with bilateral subretinal fluid.
4. BCR-ABL and ALK Inhibitors
- BCR-ABL Inhibitors: Can cause ischemic maculopathy, serous retinal detachments, and CMO.
- ALK Inhibitors: While mostly known for transient visual disturbances (like light trails), they can rarely cause posterior uveitis.
Neuro-Ophthalmic and Vascular Risks
Beyond direct retinal damage, several therapies carry risks of optic neuropathy and neuritis. ICIs can cause a unique bilateral, painless optic neuritis, while BCR-ABL, FLT3, and ALK inhibitors have all been linked to sight-threatening optic nerve swelling. Additionally, the rare occurrence of retinal vein occlusion with MEK inhibitors may serve as a critical indicator of systemic hyperviscosity or vascular risk in cancer patients.
Management and Multidisciplinary Care
Management of these posterior segment events is often complex:
- Retinopathies (like MEKAR/FGFRAR) are frequently asymptomatic and may only require monitoring without drug cessation.
- Inflammatory events (like panuveitis or vasculitis) often necessitate aggressive local corticosteroid injections (periocular or intraocular) or systemic steroids.
- Vascular occlusions generally require permanent discontinuation of the therapy.
Conclusion: Early recognition through standardized monitoring and close communication between oncologists and ophthalmologists is essential to balance life-prolonging cancer treatment with the preservation of vision.
Reference Dong, M. R., Chiu, Z. K., Lim, L. L., & Lin, M. L. (2026). Ophthalmic Adverse Events of Systemic Immunotherapy and Targeted Cancer Therapy: A Review. Clinical & Experimental Ophthalmology.


