

Although persistent placoid maculopathy (PPM) has several characteristics similar to APMPPE and macular serpiginous choroiditis (SC), it also has numerous distinguishing characteristics. The term PPM was coined in 2006, when six individuals aged 50 to 68 years were diagnosed with macular placoid lesions and a high rate of CNV development.
Patients with PPM may have a prodrome phase, including influenza-like symptoms, and the majority of patients report bilateral vision impairment, photopsia, and scotomas upon presentation.
Clinical examination reveals the lack of anterior uveitis and, in a minority of cases, uncommon vitreal cells, with the posterior pole being the primary location of inflammation.
The condition is typically self-resolving and monophasic in nature, and it always takes far longer to recover than APMPPE.
FAF results vary according on the level of RPE involvement. FA and ICGA exhibit early hypofluorescence in the active phase, remaining on ICGA and becoming hyperfluorescent on FA in the late phases, similar to the other placoids (FA–ICGA dissociation).
OCTA was used to demonstrate and validate perfusion deficiencies at the choriocapillaris level. Cross-sectional OCT results are phase-dependent and are often comparable to but less severe than those reported in APMPPE.
Cerebral vasculitis, like APMPPE, may exacerbate PPM. Thus, if any neurologic symptoms are present, neuro-imageing studies should be considered. PPM-like findings have also been found in two individuals aged 74 and 85 years with giant cell arteritis. These data imply that before to labelling a patient as PPM, systemic symptoms should be carefully considered.
Unlike APMPPE, which has multifocal lesions dispersed across the retina and often affects younger patients with a low risk of CNV, placoid lesions in PPM are exclusively situated at the posterior pole, the mean age of the patients is older, and CNV is common.
In contrast to tuberculous serpiginous-like choroiditis (SLC), where placoid lesions are often more prominent and extensive, PPM active lesions are typically more ill-defined with less opaque active margins, giving the appearance of a weaker inflammatory response driving the illness. This might explain the relatively mild influence on the outer retinal layers and hence on visual acuity initially.
Corticosteroid or other immunosuppressive therapy has been used to hasten illness recovery but does not seem to be effective in avoiding CNV over time. Intravitreal antivascular endothelial growth factor (VEGF) injections have been shown to improve results and minimise neovascular exudation in the presence of CNV. Early therapy seems to be beneficial, with return of CNV or atrophy after quiescence sometimes seen. Despite frequent injections, the formation of fibrosis may occur.

Persistent placoid maculopathy. (A, B) Fundus photographs reveal multiple ill-defined yellowish placoid lesions at the level of the retinal pigment epithelium (RPE), with the majority of lesions confined to the posterior pole. (C, D) Macular optical coherence tomography demonstrates loss of the outer retina and irregularities in the RPE. (E, F) Autofluorescence of the fundus reveals stippled hyper and hypoautofluorescence in accordance with the lesions. (G, H) Fluorescein angiography demonstrates mild and irregular late hyperfluorescence in lesions, which corresponds to larger hypofluorescent areas on late indocyanine green angiography (ICGA) (I, J). (K) One month after presentation, the right eye’s ICGA reveals a slight decrease in the hypofluorescent signal compared to the presentation ICGA (I).
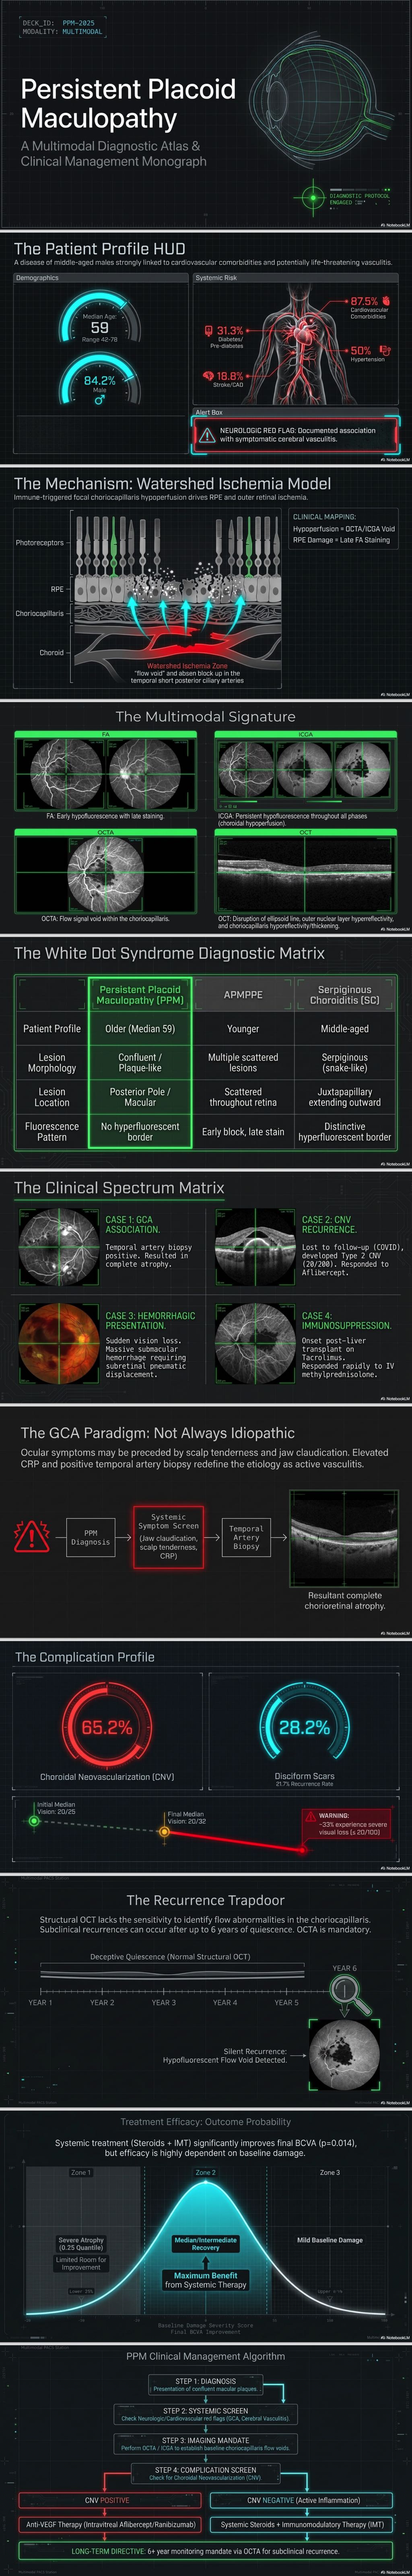
Navigating Persistent Placoid Maculopathy: Long-Term Insights and Clinical Realities
Persistent placoid maculopathy (PPM) remains one of the more challenging “white dot syndromes” for the retina specialist. Since its first description in 2006, our understanding has evolved from viewing it as a mere variant of acute posterior multifocal placoid pigment epitheliopathy (APMPPE) to recognizing it as a distinct clinical entity with a high complication rate and a often guarded visual prognosis.
Recent multicenter data and case series provide critical updates on how we should diagnose, monitor, and treat these patients.
Clinical Presentation and Differential Diagnosis
PPM typically affects middle-aged individuals (median age ~59 years), with a notable predilection for males (~84%). Patients often present with bilateral central scotomas, blurred vision, or photopsias.
Key clinical features include:
- Lesion Morphology: Bilateral, confluent, yellowish-white plaque-like lesions confined to the macula.
- Distinction from APMPPE/SC: Unlike APMPPE, PPM lesions are confluent and persistent rather than scattered and transient. Unlike serpiginous choroiditis (SC), PPM lacks the characteristic hyperfluorescent border and is primarily macular rather than peripapillary.
The Role of Multimodal Imaging
Diagnosis relies heavily on characteristic imaging findings:
- ICGA: The “gold standard” for diagnosis, showing persistent hypofluorescence throughout all phases, signifying deep choriocapillaris hypoperfusion.
- FA: Early hypofluorescence with late staining.
- OCT/OCTA: Reveals outer retinal and RPE disruption, often with a corresponding flow void in the choriocapillaris on OCTA. OCTA is particularly useful for detecting subclinical recurrences or early choroidal neovascularization (CNV).
Complications: The Rule, Not the Exception
Recent studies emphasize that PPM is far from benign, with a 73.9% complication rate.
- Choroidal Neovascularization (CNV): Occurs in approximately 65% of eyes.
- Macular Atrophy: Nearly 30% of eyes develop disciform scars or significant atrophy, leading to severe visual loss (<20/100) in one-third of patients.
- Recurrence: Reactivation can occur even after years of quiescence; one study noted a recurrence after six years.
Systemic Red Flags: More Than Just the Eye
PPM is frequently associated with systemic vascular risk factors. 87.5% of patients in a recent cohort had cardiovascular comorbidities, including hypertension and diabetes.
Crucially, specialists must be vigilant for:
- Cerebral Vasculitis: Reported in multiple PPM cases, requiring prompt neuroimaging if neurological symptoms arise.
- Giant Cell Arteritis (GCA): Case reports have linked PPM-like lesions to biopsy-proven GCA. Systemic workups, including C-reactive protein and ESR, are recommended in older patients.
Management Strategies
While no randomized controlled trials exist, statistical analyses indicate that systemic treatment is a significant predictor of better final visual acuity (p = 0.014).
- Steroids and IMT: A combination of systemic corticosteroids and immunomodulatory therapy (e.g., Azathioprine, Mycophenolate Mofetil) is often employed.
- CNV Management: Intravitreal anti-VEGF remains the mainstay for treating secondary CNV, often requiring multiple injections to stabilize vision.
Conclusion for the Specialist
PPM requires long-term, vigilant monitoring. The high rate of CNV and the potential for late recurrences necessitate the routine use of OCTA and ICGA. Furthermore, the strong association with systemic vascular and inflammatory diseases means the retina specialist plays a vital role in the patient’s broader medical management.
References
- Seppey C, Kaisari E, Anjou M, et al. Persistent placoid maculopathy: long term outcomes and prognostic factors. Retina. 2026.
- Anjou M, Bernabei F, Villaret J, et al. Different clinical presentations of persistent placoid maculopathy: a case series. BMC Ophthalmol. 2025;25:272.

